Titration automatique de l'oxygène - en situation d'urgence Marseille, COPACAMU, March 2018
←
→
Page content transcription
If your browser does not render page correctly, please read the page content below

From the white and cold Québec to Lyon …

Titration automatique de l’oxygène
          en situation d’urgence
                Erwan L’HER, MD, PhD,
     Centre Hospitalier Universitaire de la Cavale Blanche
                  LATIM INSERM UMR 1101
                           Brest, France

           Marseille, COPACAMU, March 2018
CONFLITS D’INTERET

•   Research program on mechanical ventilation and
    oxygen therapy automation : Canadian Fondation
    for Innovation (Fonds des Leaders) / FRSQ

•   Co-founder of a R&D company (OXYNOV’)
    development of automated oxygen therapy
    (FreeO2) and automated mechanical ventilation
•   GE Healthcare, Sedana and Smiths Medical:
    Fees for lectures and expertise
Eviter l’hypoxémie !

          Oxygen is the metabolic fuel !
For all patients, adults, childs, pregnancy, …etc…
Current Opinion in Critical Care 2007

Journal of Internal medicine 2013
« Oxygen »                     Many studies on
      541.731 publications since1867        physiopathology +++

             « Hyperoxia »
       7223 publications since 1945

          Pubmed - "Hyperoxia"
           Year of publications
400
350
300
250
200
150
100
 50
  0
  1940      1960     1980     2000   2020
                                                  Hafner Ann Int Care 2015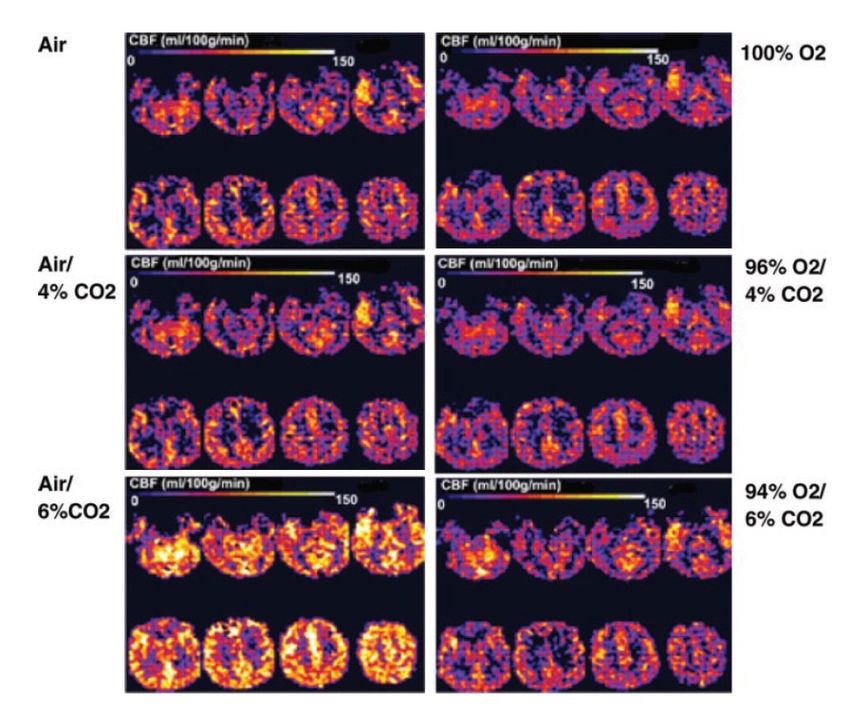
RCT 434 patients ventilés
                             ICU Mortality = 11.6%
                              SpO2 target 94-98%      PaO2 mediane
                                                      = 87 mmHg

                        SpO2 target 97-100%           PaO2 mediane
                                                      = 102 mmHg
                      ICU Mortality = 20.2%

                                               Girardis JAMA 2016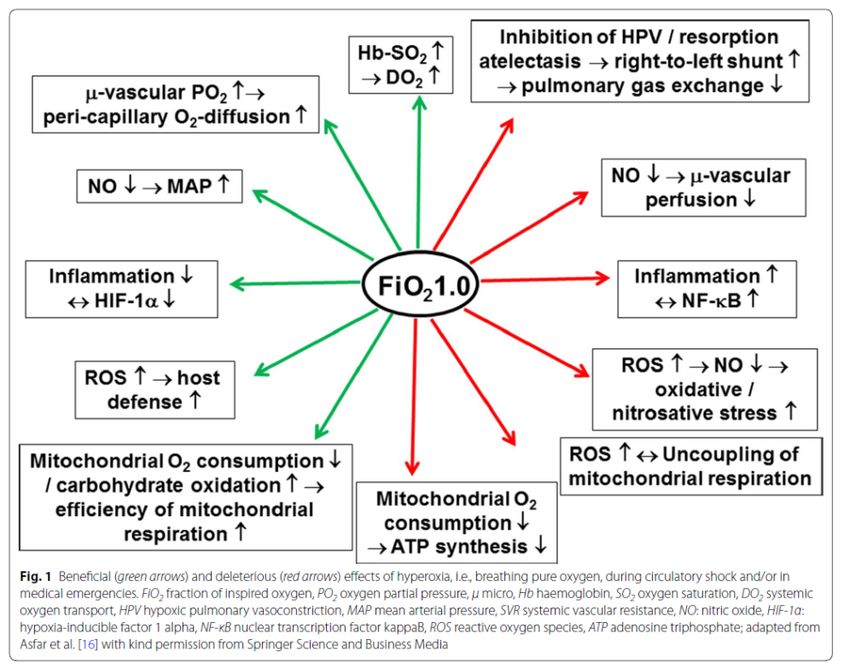
OXYDATIVE STRESS & VASOCONSTRICTION

                                                                     Hyperoxia

                                                                       ROS                  Membran lesions
                                                                                            DNA Fragmentation
                                                                                            Apoptosis
                                                           Decrease in [NO]
                                                                                            Inflammation
                                                                                            Lipid oxydation...
                                                            Vasoconstriction
                                                                        ↘ cardiac output (10-15%)
 Hyperoxia
                                                                        ↘ coronary flow (20-30%)
              Ganz Circulation 1972, Frobert CU 2004, Bak AP 2007,
                                                                        ↗ coronary resistances, vasoconstriction
              McNulthy Am J Physiol Heart Circ Physiol 2005,            ↗ cardiac enzymes
              Farquhar AHJ 2009, Cabello Cochrane 2013, Stub            ↗ infarctus size (+35%)
              Circulation 2015, Fonnes Int J Cardiol 2016
                                                                        ↗ peri-operative infarctus (2.2 vs.0.9%)
18 patients                          Room Air     100%
(stable coronary disease)
               Johnson                  15’         15’ Journal of
                        BJA 2003, Floyd JAP 2003, Floyd,
            Coronary   Blood Anesthesia
               Cardiothoracic Flow       2007, Ronning Stroke 1999,     ↘ cerebral blood flow (20-30%)
                                        45          32
               Rincon Crit (cm3/min)
                           Care Med 2014, Rincon J Neurol               ↗ mortality (stroke, TBI)
               Neurosurg
 Coronary vascular        Psy 2014, Brenner Arch Surgery 2012
                      resistances
                  (mmHg/(min/cm3))
                                       2.2         3.1
                              PaO2
                            (mmHg)
                                         73          273
               Kilgannon JAMA    2010, Bellomo Crit Care 2011,          ↗ mortality (post cardiac arrest)
               Janz Crit Care SaO
                              Med 22012, 93
                                         Ihle Crit Care
                                                     100Rescus
                                (%)
               2013, Nelskyla Scan J Trauma Resusc Emerg Med
               2013, Lee Am J Emerg Med 2014
                                                   McNulthy Am J Physiol Heart Circ Physiol 2005
CBF was measured
      7 healthy men
   by using noninvasive
    continuous arterial
spinlabeled-perfusion MRI

                            à 30% CBF reduction
                            with hyperoxia
                            (for similar PaCO2)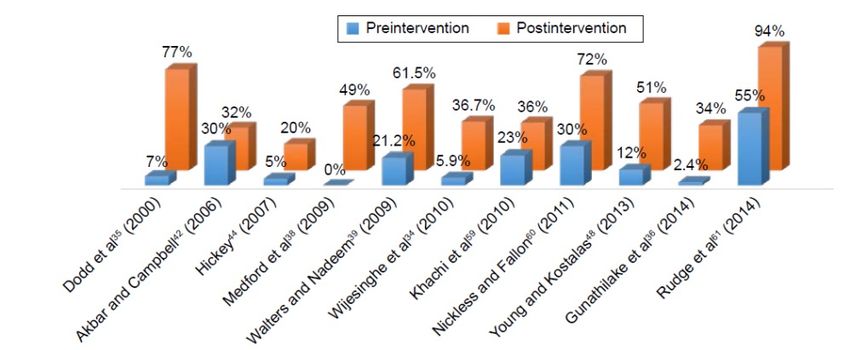
HYPEROXIA IN PATIENTS WITH STROKE

                                                 Outcome         Total     Hypoxia    Normoxia   Hyperoxia

                                                 % Death        (n=2894)   (n=1316)   (n=1084)   (n=450)

                                                  Overall         52         53         47         60*
     Minor or moderate strokes
                                                  Ischemic        48         46         47         57*

                                                   stroke

                                                Subarachnoid      44         45         38         60*
                                 without O2
                                  n=259         hemorrhage

                                                Intracerebral     59         61         54          61

                                   with O2      hemorrhage
                                 (3L/min 24h)
                                  n=292

 Ronning Stroke 1999                                            Rincon Crit Care Med 2014
Guidelines: Summary
Minimal SpO2
à 92 % (ICU) or 88% (ARDS) Jubran Crit Care 2015
à 94 % (all patients except COPD) O’Driscoll Thorax 2008
à 88% (COPD) O’Driscoll Thorax 2008
Maximal SpO2 (under additional oxygen)
à 96-98 % (ICU) or 92% (ARDS)
à 98 % (all patients except COPD) O’Driscoll Thorax 2008
à 92% (COPD) O’Driscoll Thorax 20082017
UK review of the quality of care provided to
 patients receiving noninvasive ventilation
               Initial management
Oxygen therapy is the #1 treatment in the acute care

                                     www.ncepod.org.uk
Initial management
Oxygen
88-92 in 28.6%
Below 88 in 24.4%
Above 92 in 47%
www.ncepod.org.ukOBJECTIVES OF OXYGEN THERAPY
Treating hypoxemia (Spo2 > 88 ou 94%)
Avoiding hyperoxia (Spo2 < 92 ou 98%)
Oxygen weaning
Apparently simple objectives
…but are not achieved
51%
17%
Cousins Int Journal COPD 2016INTERVENTION
September 2009
Présentations
Working groups
Protocols
Stickers….
Audit #1 Audit #2 Audit #3
June-August 2009 October 2009-February 2010 February-May 2014
102 patients 102 patients 72 patientsFlowmeter (rotameter) is a technology from
the end of XIXth century
No innovation
in the field of
oxygen
administration
…..
Utilization in the medical field for 100 years !
Maximillien Neu: 1st publication on rotameter use = 1910Oxygen flowmeter Oxymeter
Currently:
+
Oxygen flowrate
setting
Constant Variable SpO2
Oxygen flowrate
Manual adjustements
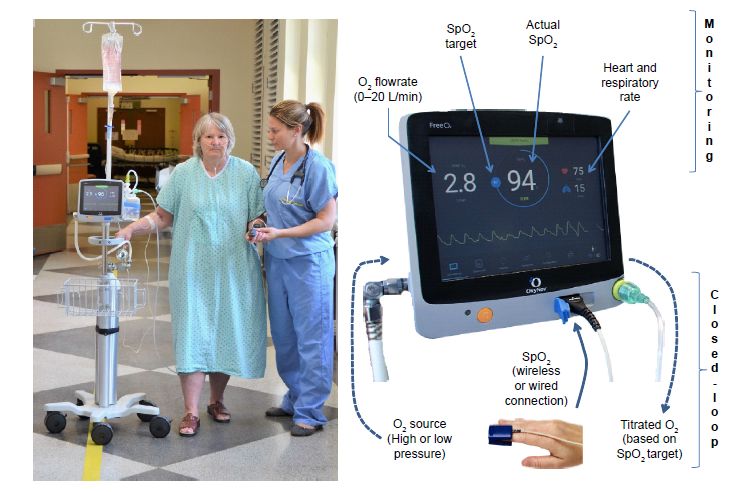
Future:
with FreeO2 Monitoring:
SpO2 O2 flowrate
The clinician set
the SpO2 target + RR HR
Trends
Variable oxygen Constant SpO2
Automated titration and weaning
Every second to maintain the target SpO2Inclusion criteria: ED admission for acute respiratory distress requiring O2≥3L/min
Exclusion criteria : O2≥15 L/min, urgent mechanical ventilation support(invasive or NIV)
Randomisation: FreeO2 or manual adjustment of O2 during 3 hours
In both groups, SpO2 was continuously recorded by the same oximeter (Nonin technology)
Primary outcome:
% of time in the SpO2 target:
88-92% (hypercapnic patients)
92-96% (hypoxemic patients)
Grants: PHRC National FreeO2 Hypox (France), MDEIE (Québec) L’Her et al. ERJ 2017RESULTS % of time in the SpO2 target
Oxygenation 120
% PRESULTS: Oxygen weaning
Partial or complete oxygen weaning
during the 3 hours study Impact on outcomes after study
45 20 FreeO2 Total
FreeO2 Total
PRESULTS FreeO2
Impact on patients outcome
ICUoftransfert
Rate ICU transfer
(%) 20
PManual Titration
(n=25)
During the whole
duration of oxygen
therapy
Automated Titration
FreeO2
(n=25)
Continuous recording Remote monitoring at nursing station
of SpO2, RR and HR (FreeO2 arm)
(both groups)
Primary outcome: Secondary outcomes:
Nurses and Physicians evaluation Oxygenation parameters (target, hypoxemia,
of oxygen and oxygen monitoring hyperoxia), duration of oxygen therapy, hospital
in both study arms length of stay
(0 to 10 scales)
Lellouche et al. International Journal of COPD 2016Lellouche et al. International Journal of COPD 2016
Economic analysis, cost/efficiency analysis
     à FreeO2 æ 20.7% cost per patient after180 days

                                   (i.e. -2959,71 Can$) (p=0,39)

       à ICER (incremental cost-effectiveness ratio)
             FreeO2 is cost effective:
(1) -96,91$ per % of time in the SpO2 target
(2) -411,09$ per % less with hyperoxia
(3) -2250,04$ per % less with hypoxemia
CONCLUSIONS
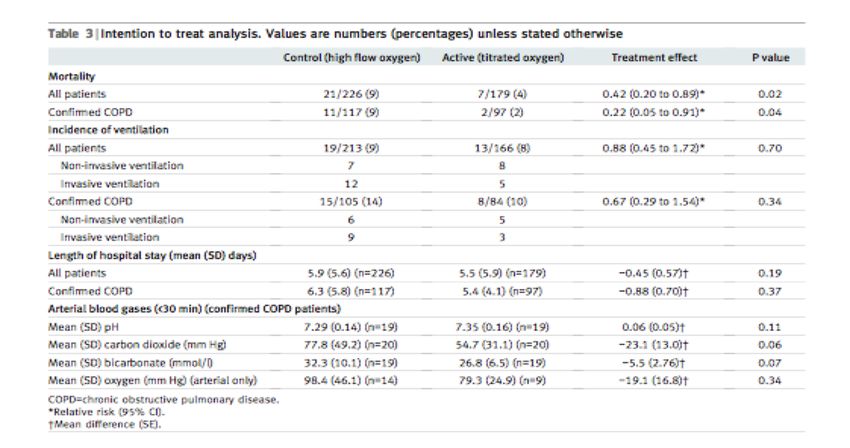
O2 flowrate should be titrated to achieve NORMOXIA
à Treating hypoxemia
à Avoiding hyperoxia
(COPD, coronaropathy, stroke, cardiac arrest, pediatry/neonatalogy….)
Automated O2 TITRATION with FreeO2 provides the
optimal dosage based on patient’s needs
Automated O2 WEANING may reduce hospital
length of stay and costs associated with acute
exacerbation of COPDClinical Cases
Typical indications
Publications under processEarly postoperative monitoring
Continuous adjustment and rapid weaning, less hyperoxia
In the recovery roomLate postoperative monitoring
Rapid response to adverse events and less hypoxemia
In the ward, following high-risk surgeryFreeO2 for oxygen adjustment under NIV Rapid response to oxygenation requirements
FreeO2 during acute coronary syndrome
Oxygenation following myocardial infarction in the CICU

 Mean inclusion duration = 11.5 ± 2.8 hours
60                                                                                                     25%
                     Manual O2 Titration                                                                                 HR 80-99   HR 100-119

                                                                          % of time with HR > 80/min
50                   FreeO2/92%                                                                        20%
                     FreeO2/97%
40
                                                                                                       15%
30
                                                                                                       10%
20
                                                                                                       5%
10                        *                                    *                                                                    * **
0                                                                                                      0%
            Time (min) with                % of patients with Premature                                         Manual    FreeO2     FreeO2
              SpO2 < 90%                      Ventricular Contraction                                                      (92%)      (97%)

     Figure 2: Mean total duration (minutes) with SpO2                                                       Figure 3: % of time with Heart
You can also read


