EMERGENCY NURSE NEW ZEALAND - NZNO
←
→
Page content transcription
If your browser does not render page correctly, please read the page content below

August | 2020

EMERGENCY NURSE
NEW ZEALAND
The Journal of the College of Emergency Nurses New Zealand (NZNO)
ISSN 1176-2691

EMERGENCY NURSE NEW ZEALAND          COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO                     AUGUST 2020

In this issue

Features

            CENNZ Honorary Life Membership                                 Embedded Earrings in Kids
     07     Award – ROSIE SIMPSON                                16

            What are the success factors for                               Post Graduate Advanced Emergency
     08                                                          32
            children with obesity having obesity                           Nursing, University of Auckland
            discussions? A cross-sectional
            multiple methods study in an
            emergency setting                                              Snippets Autumn 2020
                                                                 33

Regulars

            A Word from                                                    Regional Reports
     03                                                          17
            the Editor

            Chairperson’s                                                  College Activities
     05                                                        30-32
            Report

P2
EMERGENCY NURSE NEW ZEALAND                  COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO                                   AUGUST 2020

A Word from the Editor

Matt Comeskey
Editor | Emergency Nurse NZ
mcomeskey@adhb.govt.nz
Letters to the Editor are welcome. Letters   In contrast, another issue of concern            same old things - but better. Perhaps it
should be no more than 500 words, with       has sat like the proverbial elephant-in-         is time to push ‘pause’ on dissecting our
no more than 5 references and no tables      the-room, going nowhere and occupying            differences and re-group to focus on our
or figures.                                  an awful lot of space. There is a dis-           common goals. We need to be open to
                                             connect between the NZNO Board, its              doing things differently within NZNO in
                                             executive and the NZNO membership.               the face on an unprecedented health and
                                             It’s sadly ironic that while our nursing         economic challenges.
                                             profession pulled together to go ‘above
                                                                                              I’d like to think that NZNO – and
                                             and beyond’ to achieve unprecedented
At the time of writing the last editorial                                                     that’s all of us - would want to be more
                                             elimination of community transmission
we were staring down a crisis. What                                                           inclusive, particularly to those whose
                                             of a novel coronavirus, our professional
a difference a few months makes?                                                              voices are getting lost in the racket of
                                             body is struggling to maintain unity. All
It is worthwhile reflecting on the                                                            press releases, legal action, complicated
                                             this is happening when the core public
achievements in addressing COVID                                                              voting processes and social media posts.
                                             health message aimed at addressing the
19 to-date. These include, improved                                                           Nobody is served well when we retreat
                                             pandemic is based around altruism and
infection control, increased vaccination                                                      into separate camps and shout at each
                                             kindness. I don’t profess to understand
rates, coordination of tertiary and                                                           other. A little more kindness might make
                                             the issues or the history of this
primary level care and improved                                                               a big difference.
                                             disagreement at NZNO board level but
facilities and equipment. All of which is
                                             the reputational damage caused is self-
well covered in the regional reports in
                                             evident, public and painful.
this issue. My hope is that those gains
will be embedded in our practice and         COVID 19 lockdown has given us an
that community transmission remains          unforeseen opportunity, to reflect on how        Matt
eliminated.                                  to do new things, and how to do the

P3
EMERGENCY NURSE NEW ZEALAND                       COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO                                       AUGUST 2020

Editorial Info

Subscription:                                     Journal Coordinator/Editor:                      Natalie Anderson: RN. Doctoral
                                                                                                   Candidate & Professional Teaching
                                                  Matt Comeskey:
                                                                                                   Fellow. University of Auckland.
Subscription to this journal is through a         Nurse Practitioner, ADHB
                                                                                                   Auckland City Hospital Adult
membership levy of the College of Emergency       Email: mcomeskey@adhb.govt.nz
                                                                                                   Emergency Department, ADHB.
Nurses New Zealand - NZNO (CENNZ).
The journal is published 3 times per year         Peer Review Coordinator:                         Dr. Sandra Richardson: Dr Sandra
                                                  Matt Comeskey:                                   Richardson : PhD Senior Lecturer,
and circulated to paid Full and Associated
                                                  Nurse Practitioner, ADHB                         School of Health Sciences, University
members of CENNZ and other interested
                                                  Email: mcomeskey@adhb.govt.nz                    of Canterbury.
subscribers, libraries and institutions.
                                                                                                   Deborah Somerville: MN. Senior
Copyright: This publication is copyright in its   Peer Review Committee:
                                                                                                   Lecturer. Faculty of Medical and Health
entirety. Material may not be printed without
                                                  Margaret Colligan: MHsc. Nurse                   Sciences, University of Auckland.
the prior permission of CENNZ.
                                                  Practitioner. Auckland City Hospital
Website: www.cennz.co.nz                          Emergency Department, ADHB                       Submission of articles for
                                                  Lucien Cronin: MN. Nurse Practitioner.           publication in Emergency
                                                  Auckland City Hospital Emergency                 Nurse New Zealand.
                                                  Department, ADHB                                 All articles submitted for publication should

Editorial Committee                               Prof. Brian Dolan: FRSA, MSc(Oxon),              be presented electronically in Microsoft
                                                                                                   Word, and e-mailed to mcomeskey@adhb.
                                                  MSc(Lond), RMN, RGN. Director
                                                  of Service Improvement.Canterbury                govt.nz. Guidelines for the submission
Emergency Nurse N.Z. is the official journal                                                       of articles to Emergency Nurse New
                                                  District Health Board.
of the College of Emergency Nurses of New                                                          Zealand were published in the March
Zealand (CENNZ) / New Zealand Nurses              Nikki Fair: MN. Clinical Nurse
                                                                                                   2007 issue of the journal, or are available
Organisation (NZNO). The views expressed          Specialist. Middlemore Hospital
                                                                                                   from the Journal Editor Matt Comeskey
in this publication are not necessarily those     Paediatric Emergency Care, CMDHB
                                                                                                   at: mcomeskey@adhb.govt.nz Articles
of either organisation. All clinical practice     Paula Grainger: RN, MN (Clin),                   are peer reviewed, and we aim to advise
articles are reviewed by a peer review            Nurse Coordinator Clinical Projects,             authors of the outcome of the peer review
committee. When necessary further expert          Emergency Department, Christchurch               process within six weeks of our receipt of the
advice may be sought external                     Hospital.                                        article. CENNZ NZNO Membership:
to this group.                                                                                     Membership is $25.00 and due annually
                                                  Libby Haskell: MN. Nurse Practitioner.
All articles published in this journal remain     Children’s Emergency Department                  in April. For membership enquiries
the property of Emergency Nurse NZ and            Starship Children’s Health, ADHB.                please contact: Kathryn Wadsworth
may be reprinted in other publications if                                                          Email: cennzmembership@gmail.com
                                                  Sharon Payne: MN. Nurse Practitioner.
prior permission is sought and is credited to
                                                  Hawkes Bay Emergency Department,
Emergency Nurse NZ. Emergency Nurse NZ                                                             Design / Production / Distribution:
                                                  HBDHB.
has been published under a variety of names                                                        Sean McGarry
since 1992.
                                                                                                   Phone: 029 381 8724
                                                                                                   Email: seanrmcgarry@gmail.com

P4
EMERGENCY NURSE NEW ZEALAND                   COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO                                  AUGUST 2020

Chairperson’s
Report
                                              Welcome to the new normal – New Zealand post lock-down is
                                              confronting in many ways, while offering a mix of stimulating and
                                              difficult situations. As we come to terms with integrating social
                                              distancing, routine handwashing and limited travel options into
                                              our everyday routine this alongside a profound gratitude for the
                                              relative safety in which we find ourselves.

                                              Covid-19 response which are likely to be         still in place, and partly due to a
                                              carried forward. One of these has been the       reluctance from organisations to allow
                                              establishment of on-line CNM meetings.           staff to travel for educational or other
                                              While we have traditionally hosted a face        purposes. As a result of this, we know
                                              to face meeting to enable the sharing of         you will understand why we have chosen
                                              information and ideas, this of course was        to formally announce the cancellation of
                                              not possible during lock-down. Instead,          the 2020 CENNZ Paediatric Symposium.
                                              we commenced regular zoom meetings,              However, we do need to provide a forum
                                              to allow CNMs from around the country            to host the College AGM. While this
                                              to share information, techniques,                may not have been the favourite part
                                              responses, and pose questions or ask for         of the conference or symposium, I ask
Despite the uncertain economic future,        specific information as part of the effort       that you remember that this is essential
we have managed to maintain a degree          to share resources during the pandemic.          to enabling us to progress as a working
of control over the covid-19 pandemic         While not limited only to issues of Covid-       college. This year, the AGM will be held
which is lacking in most other countries.     19, this has certainly been a main stream        on-line, via a zoom process, and we
Despite this, emergency departments           of discussion.                                   need your support to ensure that we
remain at the forefront of any potential                                                       have a quorum of members. We will
                                              Along similar lines we hope to start a series
response, while needing to manage the                                                          be minimising this to essential business
                                              of online meetings for nurse educators,
usual challenges of winter surges, staffing                                                    only, and including a guest speaker to
                                              to address issues and share knowledge
difficulties and service overload.                                                             provide additional interesting material.
                                              around ED topics. The move to zoom has
                                                                                               The details for this (including date and
The College remains focussed on               created a greater sense of familiarity and
                                                                                               presentation topic) will follow.
supporting individual nurses, practice        willingness to use this medium, and has
settings and the wider profession as we       opened up the opportunity to develop             CENNZ has continued to advocate for
all seek to maintain the highest possible     regular interactive forums.                      responses to violence and aggression in
standards, and find solutions to the                                                           the workplace, with representation on
                                              Cancellation of paediatric symposium;            the national NZNO committee working
difficulties and demands that have
                                              need for on-line AGM                             in this area, and we continue to follow
presented during this period.
                                              We have all realised that travel is              the progress of the Protection for First
It is important to recognise the positives                                                     Responders Bill which is going through
                                              inevitably limited in the post lock-down
as well as the testing elements, and there                                                     parliament at present.
                                              period. This is in part due to restrictions
have been innovations as a result of the

P5
EMERGENCY NURSE NEW ZEALAND                   COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO                                    AUGUST 2020

Chairperson’s
Report Cont.
There are on-going questions around           Are we in a position where this would
how New Zealand and the health system         be possible? Is this part of our role? And
can best manage the influx of returning       if not, then what systems are in place to        Dr Sandra Richardson
kiwi’s, and the placement of quarantine       manage such requests? We need to act as          Chairperson
facilities. This has impact not only for      ED nurse’s always do – to be prepared,           College of Emergency Nurses New Zealand
primary healthcare staff, but also for the    and with a high index of suspicion for the
ED sector. We need to be mindful of the       unexpected.                                      Contact: cennzchair@gmail.com
importance of having clear plans and
                                              I wish you all well, and thank you once
processes for managing the ‘what if ’s’ in
                                              again for the contribution you have
regard to out breaks, to unforeseen illness
                                              always made, and continue to make to
and injury, and how to manage should
                                              the healthcare of New Zealand.
ED staff be called on to assist if current
service provision is insufficient.            Kia Kaha

P6
EMERGENCY NURSE NEW ZEALAND                 COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO                                   AUGUST 2020

New CENNZ
Honorary Member
On International Nurses Day 2020, CENNZ announced a
new Honorary Life Member to the college: Rosie Simpson,
from Dunedin.

Rosie graduated from the Dunedin            2002, Rosie stepped into the newly-              representatives. She encouraged
School of Nursing in 1975 and started       creates Associate Charge Nurse                   fellow nurses to be involved in change
working in the Dunedin Emergency            Manager role at Dunedin ED, and held             at a local and national level. As a CENNZ
Department in 1988. Where at this time      the position until 2009. Rosie then spent        member she attended a number of
she worked four nights a week, while        two years as the Emergency Planner               conferences, always willing to share her
raising a family. In 2000, Rosie became     for Dunedin Public Hospital, but missed          ideas, knowledge with her peers and be
actively involved in emergency nursing,     emergency nursing so returned to                 involved in promoting the education of
on a national level. Having completed       Dunedin ED in 2012, where she has                emergency nurses.
one of the first triage courses offered     continued to support students, graduate
                                                                                             Rosie has been a professional role-
in New Zealand, she became a triage         nurses and new nurses. Rosie was
                                                                                             model and has promoted excellence in
instructor - a position that she held       involved in the Emergency Department
                                                                                             emergency nursing within Aotearoa New
for ten years. During this time, Rosie      simulation governance group, and the
                                                                                             Zealand and is a worthy recipient for an
travelled around the country on her days    simulation suite development and
                                                                                             Honorary Life member of the College of
off, providing education for her fellow     design. She has been vocal in the need
                                                                                             Emergency Nurses New Zealand.
emergency nurses.                           to include, develop and to have access
                                            to education for nurses throughout her           Rosie retired in June 2020, and we wish
As a triage instructor, Rosie contributed
                                            30 years in the department.                      her well. Congratulations Rosie!!!
to the revision of the triage course and
development of the Triage Manual            Rosie has been an active CENNZ
and course materials and continued to       member in the southern region for
ensure the course and materials were        many years, being involved in study
kept up-to-date, for over a decade. In      days that were run by earlier regional

P7
EMERGENCY NURSE NEW ZEALAND                  COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO                                 AUGUST 2020

Author: Joanna Thomson,1,2 Teuila Percival,1,2                     Affiliations: 1. School of Nursing, University of
Losi Sa’u Lilo,3 Melody Smith1                                     Auckland, Auckland, New Zealand;
                                                                   2. KidzFirst Hospital, Counties Manukau District
                                                                   Health Board, Auckland, New Zealand;
Email for correspondence:
kirsteen.haynes@huttvalleydhb.org.nz                               3. Auckland University of Technology, Auckland,
                                                                   New Zealand.
                                                                   Joanna Thomson
                                                                   Kidz First Emergency Department,
                                                                   100 Hospital Road, Otahuhu, Auckland 2025
                                                                   Ph 64 9 2760044 Joanna.thomson@middlemore.co.nz

What are the success factors for children
with obesity having obesity discussions?
A cross-sectional multiple methods study
in an emergency setting.

Abstract:
Introduction
In New Zealand, almost 22% of children aged 2-14 are overweight and another 11% are obese. The children’s Emergency Department
(ED) was within the main hospital serving South Auckland, which has even higher rates of obesity. We set out to explore the
experience of families and Healthcare Professionals (HCP) when having an obesity diagnosis discussion (ODD) in the childrens’ ED.

Methods
Mixed method research design comprising interviews, HCP's survey and an HCP focus group. Convenience sampling was used to
recruit eight parents who had had an ODD at childrens’ ED in the previous 2-3 weeks. This article relates only to parent interviews.

Results
Most parents were unaware that their child was obese. Once identified, all parents wanted to have the healthy living discussion with
the HCP. Several factors affected parental engagement in the ODD and the these aligned with HCP's experiences. All parents were
keen to make some of the suggested lifestyle changes, yet they identified similar factors preventing them.

Discussion
Parents have demonstrated an ability to make changes to family lifestyle after a brief ODD. Positivity and non-judgemental
conversations were usually well received by parents. HCP should prioritise ODDs with families when parental engagement criteria
are met.

Keywords: New Zealand; child; obesity; discussion; HCP; parent; eating; Pacific.

P8
EMERGENCY NURSE NEW ZEALAND                   COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO                                   AUGUST 2020

What are the success factors for children with obesity
having obesity discussions? A cross-sectional multiple
methods study in an emergency setting cont.

Introduction                                                           likely converge to act as system barriers or enablers to healthy
                                                                       nutrition (Swinburn & Wood, 2013).
Childhood obesity has been recognised worldwide as a non-
communicable disease of global health concern (Shackleton,             Children who are already classified as obese require prompt
Milne et al. 2017). Obesity in childhood and adulthood is              support to mitigate current and future health burden and risk
associated with chronic illnesses affecting quality of life and        associated with obesity. This research aims to understand
early mortality (Kohut, Robbins et al. 2019). Children with            perspectives on barriers and enablers to their child’s healthy
obesity are at an increased risk of becoming obese in adulthood,       eating with parents of children who have received an obesity
and developing related co-morbidities (Lakshman, Elks et al.           diagnosis.
2012, Aarestrup, Bjerregaard et al. 2016, Ministry of Health
2016). There has been no published literature having ODDs in           Methods
an emergency department. Findings from Primary health have
                                                                       Study context and protocol
identified that both HCPs and parents find the ODD difficult
and this has led to fear and concern from the HCP, preventing          This research was conducted in an Auckland area with higher
ODDs occurring (Turner, Shield et al. 2009, Turner, Salisbury          than average childhood obesity rates. Parent/caregiver (hereafter
et al. 2012).                                                          parents) interviews were conducted between November 2018
                                                                       and January 2019.
Aotearoa/New Zealand has one of the highest levels of both
childhood and adult obesity in the world (Organisation for             Ethical approval was provided by the University of Auckland
Economic Cooperation and Development 2017). Inequities                 Human Participants Ethics Committee (UAHPEC; ref 021795),
exist in obesity prevalence rates, with rates highest among            the tertiary care provider’s Research Office, and the local
lower income groups. Ethnic differences also exist, with               hospital research group. Consultation with both Māori and
the highest rates in the indigenous Māori population and               Pasifika cultural safety research advisors occurred. Their advice
children of Pacific Islands ethnicity (Ministry of Health 2016).       was incorporated into the research design and when developing
Prevalence rates also differ by geography, with some Auckland          interview and focus groups questions.
(the country’s largest city) areas having almost double that of
the national average (Ministry of Health 2018). For the purpose
                                                                       Participants
of this paper, the term ‘Pasifika’ will be used, to describe people    Convenience sampling was used to invite parents who had
of Pacific descent, who are currently living in New Zealand.           recently participated in an obesity diagnosis discussion (ODD)
The term “recognises the diversity of Pacific nations and              with a Healthcare Professional (HCP) at the tertiary care
their inherent cultural practices, languages and history that          hospital emergency department. HCPs gave parents a ‘consent
underscore each ethnic group” (Firestone, Funaki et al. 2018).         to contact’ form after their ODD. Parents who consented
                                                                       to be contacted were telephoned by JT to explain the study
The burden of childhood obesity is not contained to the
                                                                       and arrange an interview time and location of the parent’s
New Zealand health system as societal and governmental
                                                                       choosing. Written informed consent was gained in person,
organisations are working towards healthier children, yet
                                                                       prior to conducting the interview. Recruitment continued until
progress is slow (Swinburn & Wood, 2013). In a review conducted
                                                                       data saturation was achieved (McKenna and Copnell 2019). To
six years after the 55 recommendations from the Parliamentary
                                                                       be eligible, parents needed to have conversational English.
Inquiry report of 2006-2007 (Kedgley 2007) was released, it
was found that only a handful were enacted and maintained
                                                                       Measures
(Swinburn & Wood, 2013). Healthy nutrition is fundamental
to children maintaining a healthy weight (Ministry of Health           Semi-structured interviews were conducted using an interview
2016). Parents are ultimately the gatekeepers to their child’s         guide. JT led the interviews and a research assistant experienced
nutrition, and play an essential role in their child’s nutrition       in conducting research with Pasifika parents (LS), attended as
behaviours (Bradbury, Chisholm et al. 2018). Yet, nutrition            many interviews as possible to ensure cultural safety. Before
behaviours do not occur in isolation and are not limited to the        the interview began, a karakia was said over the food and
family environment. Social norms, environmental prompts                time together. Upon completion of the interview, the research
and barriers to eating well, and economic and pragmatic issues         participants were given a $20 petrol voucher and $50 Countdown

P9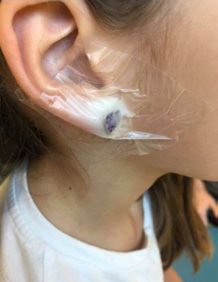
EMERGENCY NURSE NEW ZEALAND                  COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO                                  AUGUST 2020

What are the success factors for children with obesity
having obesity discussions? A cross-sectional multiple
methods study in an emergency setting cont.

voucher (local supermarket) as an acknowledgement of their            Understanding the complex and multi-faceted barriers
time and travel costs. Brief notes were taken by JT and LS            to making healthy changes
during the interviews. A reflective diary was also written by
                                                                      Themes generated from the inductive analysis centred on
JT describing the researcher’s emotions during the parental
                                                                      identifying current unhealthy behaviours and then barriers
interview data collection and thematic analysis.
                                                                      to supporting healthy behaviour changes. These barriers were
Analysis                                                              complex, multifaceted, often inter-linked and present across a
                                                                      range of social and environmental layers. Fundamentally, the
Interview data were analysed thematically following Braun and
                                                                      key themes centred on the fact that behaviour change strategies
Clarke (2008) six steps of thematic analysis. Firstly interviews
                                                                      were often occurring in isolation (e.g., focusing on the child
were transcribed verbatim by JT, read and reread in order to
                                                                      or immediate family only, with little external support). These
gain understanding of participants’ views and experiences
                                                                      often combined with the normalisation of consumption of
at the group level (Graneheim and Lundman 2004, Elo and
                                                                      unhealthy foods. The downstream impacts made sustained
Kyngäs 2008). Notes taken were utilised to provide additional
                                                                      behaviour change and improvements to child health almost
context or detail where required. The data were then organised
                                                                      impossible.
through open coding, creating categories and abstraction
(Graneheim and Lundman 2004, Elo and Kyngäs 2008). Next,              Social support and the essential role of the extended family
data were examined for themes which had an underlying
                                                                      Most of the families interviewed reported that grandparents
meaning, linking different categories together. JT and MS then
                                                                      and extended family members had an active role in their child’s
discussed the analysis and sought agreement. Co-researchers
                                                                      daily life and child care. During these times, the grandparents’
may come up with different interpretations, due to subjective
                                                                      normal food of choice for the grandchildren mainly consisted
perspectives, in which case discussion occurred to reach a
                                                                      of unhealthy foods including fast foods, takeaways and those
mutual agreement (Graneheim and Lundman 2004). For this
                                                                      with high sugar content for afternoon tea or dinner. Parents
research, decisions regarding this step was documented in
                                                                      brought up the difficulty in changing this normal pattern in
the writing up, as part of reflexivity, increasing strength in
                                                                      terms of food given by grandparents. Parents emphasised that
credibility of the qualitative research (Baxter and Eyles 1997).
                                                                      they had tried to change the food habits of the grandparents or
Once themes had been reviewed, they were named and coding
                                                                      extended family. They had tried teaching grandparents about
was completed. Finally, excerpts from the participants were
                                                                      healthy afternoon tea snacks and meals and suggested either
identified to support the themes being discussed.
                                                                      healthier options for takeaways or advising the grandparents
                                                                      to eat at home rather than take the children out for dinner.
Results
                                                                      Parents had reported difficulty in getting grandparents to
All parents who were invited agreed to participate and attended       grasp or understand the magnitude of the obesity diagnosis for
an interview (Figure 1). Data saturation was reached after            the child, thus the need for changes to food intake. This issue
eight interviews, as no further data or insights were revealed        was highlighted in the majority of the families, and caused
by the parents (McKenna and Copnell 2019). Children were              the parents stress and worry. The parents reported that they
all between eight and twelve years old, with majority males.          needed and wanted a relationship between the grandparent
Family 8 included the mother (P8) and the older sister (S8),          and the grandchild/children, but recognised that the issue of
around 20 years old, who was present during the ODD, and              unhealthy food consumed during the time together needed to
helps the mother care for the child on a day-to-day basis.            be addressed and changed to promote a healthier lifestyle for
Interviews occurred between 4-71 days (median 16.5 days)              the children.
post the ODD, and lasted between 26-185 minutes (median 50
                                                                         P3. So, what my Dad does, is some mornings, he buys them
minutes). Parents self reported ethnicity, with all but one family
                                                                         pies to eat, and then some evenings when he drops them off
identifying as Pacific, with one identifying as Māori. There is
                                                                         [to school], he buys them hot chips or butter chicken, sauce
recognition that not all families who identify as Pacific are a
                                                                         and stuff, [giggle]. I don’t know, I keep telling him, please
homogeneous group, yet strength comes from similar findings
                                                                         will you try… [healthy options]. Or else he will bring them
from these families.
                                                                         boxes and boxes of pies or doughnuts, creamy doughnuts
                                                                         and muffins and… yeah, my boys enjoy those.

P 10
EMERGENCY NURSE NEW ZEALAND COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO AUGUST 2020
What are the success factors for children with obesity
having obesity discussions? A cross-sectional multiple
methods study in an emergency setting cont.
P2. Like, my brothers and sisters and my in-laws, and when While parents found it difficult to encourage children to eat
they see my kids, they think, ‘Aahhh lets go and buy a healthy food at home, their control over what children ate at
chocolate, or you want chicken and chips? Or what you want school was even lower. Parents reported the importance of
to eat?’ kind of thing. their child eating food during the school day. This led to some
parents providing children with unhealthy food options in their
Parents discussed a mixture of feelings such as exasperation,
lunchbox, knowing that this would be eaten, rather than letting
failure and concern when having these discussions with
the child go hungry
extended family members, particularly their parents’. Parents
reported the difficulties arose as it was not culturally acceptable P5. He will have like 3 different kinds of fruit [in his lunchbox]
to question elders, particularly their parents and I guarantee you that he’s never eaten them, but they are
always there. And then not so good stuff, but just so he has
P7. I cannot say no to kids or Grandma. Yeah, because
something.
sometimes, I feel like I will upset my Mum, because I don’t
like her to do that to my kids, it is too much, like, you know P5. So, I’m like, as long as you eat… I’m OK, you know... so
feed them... that’s why their weight goes high. that’s where we are at… yeah…
P7. Very hard, yeah, coz they are my parents, and I can’t tell P3. It was like a happy thing to see him eat.
them ‘stop that’. Na, I can’t do that.
Time scarcity and accessibility and availability of unhealthy
Conversely, some parents discussed the changes towards a food options
healthier lifestyle with their parents and reported that she felt
able to trust the grandparent to mirror what the changes she Parents acknowledged that when they were time poor, they fed
had made at home. children easy-to-grab fast food. In these instances, quantity
of energy, rather nutritional quality of food, was prioritised.
P5. Yeah, she [Grandma] does it, [what Mum does at home], There was discussion about the differences between living in
and then she makes sure that everyone else has it as well. So, the [Pacific] Islands and in New Zealand with respect to the
he is not singled out, so whatever he can have, everyone else food available. Parents highlighted that there was easy access
has, so she is into everything. She is really good, and it makes to takeaways in New Zealand, which served parents well when
it a whole lot easier. they were rushed, due to the day-to-day business of life.
Some parents highlighted that once they had heard the P2. ‘It was just me, [going to] university and then doing the
information at the ODD there were differences between the kids trainings and trying to work at events and stuff, and
parents of the child as to the importance of making changes to it all got too much, so I would always pack, you know, the
the child’s lifestyle. cheapest, the fast food, whatever I could get that would
P2. So, my partner [C2’s father] … this is his first son, so he feed them, until I had finished my meetings or finished
was thinking… he was thinking along the lines of, it is ok, it whatever I was doing to cover them… and they are not going
is our his first born, you know, my first baby, my first son. He to interrupt me, you know, they are going to be hungry and
can eat whatever he wants, treat him like a king. then people are going to look at me and say “why aren’t you
feeding your kids?”
P3. [We, the parents are] Not on same page. That was my
struggle this week, because yeah… I tried to serve my kids the P8. [In NZ] The veggies are expensive, the fish is expensive,
right amount of food, and then he [Dad] says to them, have so we are going to resort to cheaper meals and takeaways
some more, don’t worry about it, or he’ll say, erm… is that all and all.
that the kids are eating? And I say yup. Obesity (and the downstream consequences) as a rite
Child preferences for unhealthy food of passage
Children, themselves, also played a role in determining the food Normalisation and acceptance, even a parental desire to want
they ate. Parents expressed concern due to an inability to get the a larger child was discussed frequently. There was recognition
children to eat vegetables, in a range from any to advised quantities. from the parents that part of this was cultural. Yet there was
P 11EMERGENCY NURSE NEW ZEALAND COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO AUGUST 2020
What are the success factors for children with obesity
having obesity discussions? A cross-sectional multiple
methods study in an emergency setting cont.
no discussion as to what it meant for the child’s health and I want to snack, yeah. So, it will be good for him, in the
longevity, prior to the ODD. The normality and desire for a family with his cousins and stuff, let them explore something
larger child was reinforced by grandparents and sometimes at different instead of having a big meal and just being so lazy.
church or within their social group. And it affects them in the long run.
P3. That is what really got me [that he was heavier than me, Food was identified as a very important cultural component
when he stood on the scales] … but normally people are like... of being in a Pasifika family. Food’s importance came from
‘O my God, he is sooo chubby’, it was like… I loved it. I loved its link with bonding time with family members and rewards
it. That my kids were chubby, like... you know... like... and or methods of expressing love; it was not seen exclusively as a
I didn’t want my baby to lose like... I didn’t want them to nutritional component of a healthy lifestyle. This meant that,
[reduce their] weight… for some families, on a daily basis, much emphasis was put on
the children eating with the extended family. Parents reported
P5. You know so from when he was born, he was born, he
that the children would receive large portion sizes, with not
was born big. He is big for his age... like in my culture, in
much attention put into providing healthy meals or snacks for
comparison with my family, that is like our normal. He is
the children.
actually small in our family, like weight wise’. [Dad’s family]
they are like … ‘Ahh we need to feed you’. They think he is P7. My Mum and my sister, they don’t have any kids. Only
too small. Like in my family, he is... he is just like all the other me have kids. They give them like coke, chips, chocolate all
kids. He is bigger and he is taller than all the other kids, than the time. Takeaway, McDonald’s, KFC. Yeah, they always go
my sister’s kids, but they are all European, but erm... but he outside [to] eat, every day.
does not look overly big, just tall, you know, nothing out of
the norm, like with my brothers and sisters and their kids. Relationships with extended Pasifika family and food
Some parents were aware Pasifika people living in New Zealand
Pacific relationships with food culture as both barriers and
are represented negatively in health statistics. Knowing this,
opportunities
Parent 8 had a desire for this not to be the case for her family.
Many parents attributed lifestyle around food choices being
S8. Mum said that we are not going to be like that [poor
intrinsically related to cultural practices and their wider
Pacific Island statistic]. She said “we should not just do the
community. This cultural aspect came from both the parents
whole ‘leave it, she will just grow out of it…’ lose the baby fat
who were of Pacific Island descent born in New Zealand,
type of mentality. And if we start doing that, then when she
and some who had been born and lived in the Islands, then
becomes older, it will be harder for her, where you said you
immigrated to New Zealand. Most of the parents interviewed
should not be like... Food isn’t everything. You should eat to
had their parents, who had been born and brought up in the
live, not live to eat”.
Pacific Islands, living in New Zealand. Parents reported that
there was direct cultural conflict between the lifestyle that the Parent 4 identified with her Māori culture. She discussed her
parents or grandparents had been brought up with overseas journey of learning the Māori culture, as an adult, and what this
and the New Zealand lifestyle. This is intermingled with the meant for her. She referred to the values of respect and dignity.
value placed on children and spoiling them with food, while When applied to food she said:
they are young.
P4. It is about respect, respect, about others respecting self.
Parent 2 reported that healthy food was not the normal in her But how do we do that, with food? With kai? It is love. Yeah,
extended family, and she has used the ODD as an opportunity you know respecting the things, we karakia [prayer] over the
to educate the extended family around healthier food options. food that we have.
P2. Yeah, being in the Pacific family, we always turn around P4. ‘Because life matters, quality of life. And all its aspects is
and screw our nose up at stuff that is healthy… So, my in laws a gift, and it is about respecting this life we have, the food we
[do]. I live around people who are like ‘why is there olives in have, our body. My body.
here, why is there lettuce? And I just say, it is just for when
P 12EMERGENCY NURSE NEW ZEALAND COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO AUGUST 2020
What are the success factors for children with obesity
having obesity discussions? A cross-sectional multiple
methods study in an emergency setting cont.
The conflict that these parents have expressed seems to indicate her children to Movies in the Park, a free event at a Māori
that maybe there are conflicting values as a parent particularly university, where there were only unhealthy food stalls.
with respect to food. Conflict identified here is around the
P8. But it does not help when you go to Movies in the Park,
nourishment that the food provides and also the role of the
and everything is around there for the children. Then the
mother who wants to demonstrate her love to her child through
children walk past and saw her and were ‘Wow, I want one
food.
of that Mummy!’ [candy floss]. Even me, I felt bad, I said
P4. My love language is quality time. In that quality time, ‘Damn it, buying it for her, just because she wants it, and
food is how I love my kids, so being respectful of what we are what am I advertising to the other families, and to the other
eating, erm, the times we are eating, eating together children. You know, educational and awareness out there.
The Wãnanga put up that Movie in the Park, why don’t they
P4. Food… not matter what the event. Love them with the
put up a healthy fruit stalls for free?
food.
Easy access to, and normalisation of, unhealthy foods Discussion
There was discussion on some of the differences between ‘living The aim of this research was to understand perspectives
in the Pacific Islands’ and in New Zealand with respect to the on barriers and enablers to their child’s healthy eating with
food available. The focus of the discussion was on the easy parents of children who have received an obesity diagnosis. Key
access to takeaways in New Zealand and the more rushed day- findings were that a range of barriers existed across the socio-
to-day life which required quick meals. ecological spectrum, including social norms and relationships,
environmental factors, and time and financial barriers. Parents
Parents also pointed out the cost of fresh fruit and vegetables discussed many problems that they faced with their children
and the accessibility in South Auckland. For Parent 2, the cost particularly with the child’s desire for treats and being spoilt by
of fresh fruit and vegetables was not a hindrance, but was new extended family members. Parents reported that the extended
concept for her to start buying vegetables every few days. Parent family continued to give treats to the children, either with fast
8 reported that the high cost of fresh fruit and vegetables was foods during contact time or lollies, even after being explicitly
prohibitive to her providing enough for her family on a daily requested not to do so by the parents. Further examination on
basis. the nature or reasons for grandparents spoiling the children
P2. I don’t think so, I think it’s… because if I can afford fast was not discussed within this research.
food, I can afford fresh veggies. I know it goes off, but I like It could be concluded that a level of parental resilience is
to pick different varieties, so that I know… So I’ll pick say, a required to overcome child demands and negotiating with
lettuce, and it will last us say 2-3 days max, and when that family members. This aligns with the notion of ‘pester power’
lettuce has gone, I’ll quickly grab something else to replace (Mikhailovich and Morrison 2007). In working with families,
it, so I just buy as it goes. HCPs might need to acknowledge that this could happen. This
P8. Yeah, like here fish is expensive, veggies, the type of might support parents by making them aware of the need to
veggies we eat here is not the same… Financially you cannot build resilience and strategies to bring the child on board with
afford the healthy… You know, OK we had healthy meals, but the journey deal with children pushing for unhealthy treats or
it is much healthier here [in New Zealand]. The veggies are being resistant to an activity.
expensive, the fish is expensive, so we are going to resort to The parental need for support in this journey has been found
cheaper meals and takeaways and all. in a study which documented of the struggle of the ‘lead parent’
The environment where they lived or the area the children when having to battle the extended family who undermine their
went to school was not supportive of healthy food options. actions (Stewart, Chapple et al. 2008). Usually, parents reported
This was demonstrated by parents reporting hot chip shops that still the grandparents were found to have undermined the
and unhealthy cheap foods so close to the schools. This lead parent both verbally and physically, in changes towards a
was encapsulated by Parent 8’s frustration when she took healthier lifestyle. In future, parents may need further support,
P 13EMERGENCY NURSE NEW ZEALAND COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO AUGUST 2020
What are the success factors for children with obesity
having obesity discussions? A cross-sectional multiple
methods study in an emergency setting cont.
after an ODD to keep their resolve strong. The parents might within the HCP focus group were around the awareness over
also need strategies to help communicate with grandparents differences between Pacific culture and westernised beliefs
and bring them on board with the healthy lifestyle, as well. surrounding body size and health
Stewart, Chapple et al. (2008) also recorded it was difficult for
The quotes from the parents showed the pull between Pasifika
the parents to have the discussion with grandparents, with
people’s cultural desire for bigger children and healthy children,
respect to asking them not to feed children certain foods, as
as thinness was often equated with ill health (Firestone, Funaki
demonstrated here. Although this was discussed in the current
et al. 2018). It could be determined that prior to the ODDs,
study’s interviews, a solution was not apparent. A solution
the parents interviewed for this research were unaware of the
to developing support for parents and families must include
detrimental effect that higher BMIs could have on the child’s
allowances for those who have time pressures or children who
health. This was an uncomfortable discovery for most parents
pester them.
and caused distress. The latter was due to the conflict between
Parents spoke about the difficulty of holding conversations previous thoughts on increased food intake for their child and
with grandparents about making changes as this could seem new realisations of potential long-term health complications.
disrespectful and, in any event, appeared to have little effect.
Firestone, Funaki et al. (2018) conducted focus groups
These findings align with previous evidence showing that
discussing health and well-being with Pasifika people. It was
parents need family support to maintain changes. Stewart,
found that they identify with a unique and strong sense of
Chapple et al. (2008) undertook 17 interviews with parents
well-being. Pasifika well-being is associated with the well-being
who had completed a six-month intervention programme, in
of the “family unit”, as opposed to the “individual being sick”.
Glasgow; they found that the lead parent, usually the mother,
“Health” was found to be a state of “doing”, that is, having a
needs support from someone outside the family to continue to
work-life balance which leads to a healthier lifestyle. It also
motivate the child. They also found that the lead parent needs
includes “feeling motivated and a healthier life” embracing the
help as other family members continue to offer treats and
physical and mental well-being of the family unit (Firestone,
undermine the parent’s action and lifestyle changes. These
Funaki et al. 2018). This could be applied to these findings,
findings also support the current study, which found that many
with recognition that Pasifika do not view health and well-
of the parents said that they had difficulties with their partners
being in the traditional western views. HCPs might be better
or grandparents understanding the need for both the changes
able to understand the Pasifika’s holistic view of the child
and ongoing support for the mother on this journey.
within the family as demonstrated by the use of ‘weight’ per
Eli, Howell et al. (2014) interviewed parents and grandparents se was not a specific health determinant for Pasifika people,
regarding body weights and found they reported on the whereas increased childhood weight indicated poorer health
difficulty of having intergenerational discussions on a child’s outcomes for westernised families. Health for Pasifika families,
weight. This equates with the findings of the current research. is measured by a desire to live longer so as to look after the
Whereas Eli, Howell et al. (2014) reported on difficulty in next generation. The desire for parents to make a change to the
words used in discussing weight with their child/grandchild, child’s current lifestyle, could be related to the desire for the
the findings from this research are around a parent engaging child to live longer.
the grandparent in understanding the health risks associated
with continuing current lifestyle choices, mainly in relation to Conclusion
food. Further research in this area might yield better advice for
Parents care passionately about their children. Universally,
parents to enable these discussions.
these parents were able to associate obesity with being
Parents’ reported their rationales were cultural and generational, unhealthy and they did not want this for their child. Parents
with grandparents specifically wanting larger grandchildren. valued the ODD which enabled them to reflect on current
Parents reported that traditional Pacific culture demanded that lifestyle practices that they employed, that they now realise to
larger children were wanted without awareness of determinants be unhealthy, and were making changes. Changing children’s
of health. Discussions in Firestone, Funaki et al. (2018) and nutritional behaviours was commonly discussed by parents.
P 14EMERGENCY NURSE NEW ZEALAND COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO AUGUST 2020
What are the success factors for children with obesity
having obesity discussions? A cross-sectional multiple
methods study in an emergency setting cont.
Several families discussed difficulties and challenges such to start making changes after a very short ODD. Comprehensive
as the cost of food, time, extended family, and cultural and approaches that support families in their journey to healthy
social norms. These difficulties are similar to those previously nutrition are urgently needed.
identified and published yet this study showed parents were able
Organisation for Economic Cooperation and Development. (2017). Obesity update 2017. Retrieved from
References
https://www.oecd.org/els/health-systems/Obesity-Update-2017.pdf
Australasian College of Emergency Medicine (2001). Guidelines for Implementation of the
Shackleton, N., Milne, B. J., Audas, R., Derraik, J. G. B., Zhu, T., Taylor, R. W., . . . Taylor, B. (2017). Improving
Aarestrup, J., Bjerregaard, L. G., Gamborg, M., Ängquist, L., Tjønneland, A., Overvad, K., . . . Baker, J. L. rates of overweight, obesity and extreme obesity in New Zealand 4-year-old children in 2010-2016.
(2016). Tracking of body mass index from 7 to 69 years of age. International Journal of Obesity, 40, 1376. Pediatric Obesity, 22, 22. doi: https://dx.doi.org/10.1111/ijpo.12260
doi:10.1038/ijo.2016.88 https://www.nature.com/articles/ijo201688#supplementary-information
Stewart, L., Chapple, J., Hughes, A. R., Poustie, V., & Reilly, J. J. (2008). Parents’ journey through treatment
Baxter, J., & Eyles, J. (1997). Evaluating qualitative Research in Social Geography: establishing ‘rigour’ in for their child’s obesity: a qualitative study. Archives of Disease in Childhood, 93(1), 35 - 39. doi:10.1136/
interview analysis. Transactions of the Institute of British Geographers, 22, 505-525. adc.2007.125146
Bradbury, D., Chisholm, A., Watson, P. M., Bundy, C., Bradbury, N., & Birtwistle, S. (2018). Barriers and facil- Swinburn, B., & Wood, A. (2013). Progress on obesity prevention over 20 years in Australia and New
itators to health care professionals discussing child weight with parents: A meta-synthesis of qualitative Zealand. Obesity Reviews, 14(2), 60 - 68. doi:10.1111/obr.12103
studies. British Journal of Health Psychology, 23(3), 701-722. doi:10.1111/bjhp.12312
Turner, K. M., Salisbury, C., & Shield, J. P. H. (2012). Parents' views and experiences of childhood obesity
Braun, V., & Clarke, V. (2008). Using Thematic Analysis in Psychology. Qualitative Research in Psychology, management in primary care: a qualitative study. Family Practice, 29(4), 476-481. Retrieved from https://
3(2), 77-101. Retrieved from https://www.tandfonline.com/doi/abs/10.1191/1478088706qp063oa cmdhb.idm.oclc.org/login?url=http://search.ebscohost.com/login.aspx?direct=true&db=c-
Eli, K., Howell, K., Fisher, P. A., & Nowicka, P. (2014). "A little on the heavy side": a qualitative analysis of cm&AN=104363714&site=ehost-live&scope=site
parents' and grandparents' perceptions of preschoolers' body weights. BMJ Open, 4(12), e006609. Turner, K. M., Shield, J. P. H., & Salisbury, C. (2009). Practitioners' views on managing childhood obesity
Retrieved from http://ovidsp.ovid.com/ovidweb.cgi?T=JS&CSC=Y&NEWS=N&PAGE=fulltex- in primary care: a qualitative study. British Journal of General Practice, 59(568), 856-862. doi:10.3399/
t&D=med8&AN=25500371 bjgp09X472269
http://openurl.auckland.ac.nz/resolve?sid=OVID:medline&id=pmid:25500371&id=-
doi:10.1136%2Fbmjopen-2014-006609&issn=2044-6055&isbn=&volume=4&is-
sue=12&spage=e006609&pages=e006609&date=2014&title=BMJ+Open&atitle=%22A+lit-
tle+on+the+heavy+side%22%3A+a+qualitative+analysis+of+parents%27+and+grand-
parents%27+perceptions+of+preschoolers%27+body+weights.&aulast=Eli&pid=%3Cau-
Figure 1. Consent to contact forms leading to interview flow chart:
thor%3EEli+K%3BHowell+K%3BFisher+PA%3BNowicka+P%3C%2Fauthor%3E%-
3CAN%3E25500371%3C%2FAN%3E%3CDT%3EJournal+Article%3C%2FDT%3E
Elo, S., & Kyngäs, H. (2008). The qualitative content analysis process. Journal of Advanced Nursing, 62(1), 30 consent to contact forms printed
107-115. doi:10.1111/j.1365-2648.2007.04569.x
Firestone, R., Funaki, T., Dalhousie, S., Henry, A., Vano, M., Grey, J., . . . Ni Mhurchu, C. (2018). Identifying
and overcoming barriers to healthier lives The Journal of Pacific Research, 21(2), 54 - 66. doi:10.26635/
phd.2018.913
Graneheim, U. H., & Lundman, B. (2004). Qualitative content analysis in nursing research: concepts, pro-
cedures and measures to achieve trustworthiness. Nurse Education Today, 24(2), 105-112. doi:10.1016/j. 12 consent to contact forms 1 excluded as boy was
nedt.2003.10.001 given out 15yrs and no parents
Kedgley, S. (2007). Inquiry into Obesity and Type 2 Diabetes in New Zealand. Retrieved from https://
www.parliament.nz/resource/en-NZ/48DBSCH_SCR3868_1/0dc21f5e18be663253b-
73066c4e12a418a62944f
Kohut, T., Robbins, J., & Panganiban, J. (2019). Update on childhood/adolescent obesity and its sequela.
Current Opinion in Pediatrics, 31(5), 645-653. doi:10.1097/MOP.0000000000000786
Lakshman, R., Elks, C. E., & Ong, K. K. (2012). Childhood Obesity. Circulation, 126, 1770-1779. doi:10.1161/ 11 families contact attempted Aunty was carer and lives
in Taupo
CIRCULATIONAHA.111.047738
McKenna, L., & Copnell, B. (2019). Understanding how research is done. In Fundamentals of Nursing and
Midwifery Research. A practical guide for evidence-based practice (pp. 37 - 56). Australia: Allen & Unwin. Phone number unavailable
Mikhailovich, K., & Morrison, P. (2007). Discussing childhood overweight and obesity with parents: a
health communication dilemma. J Child Health Care, 11(4), 311-322. doi:10.1177/1367493507082757 Initial contact made and then
phobe number disconnected
Ministry of Health. (2016). Clinical Guidelines for Weight Management in New Zealand Children and Young
People. (ISBN: 978-0-947515-95-9). Wellington: Ministry of Health Retrieved from https://www.health.
govt.nz/system/files/documents/publications/clinical-guidelines-weight-management-nz-chil-
dren-young-people-dec16.pdf
Ministry of Health. (2018). New Zealand National Health Survey Regional Data Explorer. Retrieved 8 interviews completed
from https://minhealthnz.shinyapps.io/nz-health-survey-2014-17-regional-update/_w_b4bb-
da38/_w_796994bd/#!/compare-regions. https://minhealthnz.shinyapps.io/nz-health-survey-
2014-17-regional-update/_w_b4bbda38/_w_796994bd/#!/compare-regions
P 15EMERGENCY NURSE NEW ZEALAND COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO AUGUST 2020
Embedded Earrings in Kids
On occasion you will encounter a child with an earring stuck in their ear lobe.
This most commonly occurs in girls younger than 12 years of age.
Assessment
Typically, at least part of the earring is visible or palpable. It is common to see the back
of the earring +/- with butterfly attached
The stud is usually buried in the ear lobe itself
The area may be tender to the touch
with localised redness and swelling
Analgesia Removal
- Apply Ametop to the back of the • A quick clean with chlorhexidine
earlobe (by default often covers the
• Make a small incision in the posterior
front too)
portion of the ear lobe. Never make an
- Consider continuous flow nitrous incision to the front for aesthetic reasons
for younger patients
• Use small alligator/artery forcepts
- Local infiltration can be used for to remove the embedded earring
older kids, or you could consider
just using cold spray
Outcome:
Once the earring is removed, the area can be dressed with a simple dressing i.e. small Primapore (island dressing) cut to size
Leave the incision to heal by secondary intention
Oral antibiotics are not needed after removal of an embedded earring from the ear lobe. NB: earrings removed from
the helix should have a 5 day course of ABx i.e Ciprofloxacin, which will cover Pseudomonas Aeruginosa
Usually takes 6-8 weeks for the site to heal
Re-piercing may be possible after this
Kathryn Johnson NP
Starship Children’s Emergency Department
P 16EMERGENCY NURSE NEW ZEALAND COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO AUGUST 2020
Regional
Reports
Northland/Te Taitokerau | Auckland
Midland | Hawkes Bay/Tarawhiti
Mid Central | Wellington | Top of the South
Canterbury/Westland | Southern
Vacancy
The position representing
Hawkes Bay/Tarawhiti
on the CENNZ National
Committee is currently
vacant.
Please see application
information on
page 23
P 17EMERGENCY NURSE NEW ZEALAND COLLEGE OF EMERGENCY NURSES NEW ZEALAND - NZNO AUGUST 2020
Northland/Te Taitokerau Region
My last report seems a lifetime Operationally, in ED the green and
rather than a few months ago. Our red zones are merging. Potentially
people did an amazing job, rising infectious presentations are placed
to meet the recent challenges with in single cubicles as much as
energy and all the resources that we possible, and aerosol-generating
could recruit or develop. May this procedures continue to require
teamwork continue to flourish not negative pressure cubicles. Slowly,
only in ED but across the hospitals processes are returning to business
and communities. as usual - or the new business as
usual. Emergency Q continues to
Self-awareness of our well-being
be an option offered for appropriate
can help us to access the supports
presentations.
to manage issues and to be aware
of our colleague’s situations. ED Community COVID testing clinics
Sue Stebbeings
piloted the Mayo Well-being Index are likely to stop by the end of July.
Nurse Practitioner in February this year, which has now Medical centres and iwi providers
Emergency Department been rolled out across our DHB. Staff will continue swabbing as necessary.
can monitor their well-being through It remains to be seen if this will
Whangarei Hospital
regular quick surveys, and resources increase ED presentations.
Contact: sstebbeings007@yahoo. are available to explore. Another
Recently there has been increased
co.nz well-being initiative promoted
acuity in ED presentations amongst
in our department just before
the 30 – 65 year age group. Usual
COVID19 was the Workplace Well-
respiratory illnesses are more visible
being at Emergency Departments
now that social distancing is less
(https://www.woweated.com/)
of a thing. Sadly, we have also seen
which aims to measure and facilitate
the evidence of increased aggression
improvement in staff well-being.
and stress in the community with
Data analysis from the staff surveys
more family violence presentations,
is underway.
and an escalation in aggressive
I attended one of the COVID behaviours from patients and
debrief sessions arranged across families. We have CCTV cameras
Whangarei Hospital. The session covering many areas of the
focused on personal factors, not department and more to be installed
operational processes. It was a to improve visibility of the area,
valuable opportunity to listen to particularly at night. Our security
the facilitator offering an outside alert has been updated so that a
perspective and uncovering impacts silent alarm can be sent directly to
that I had not considered amongst security staff from 4 points – 3 at
the small ED group present. We are front of house / triage. Plans are
so-often focused on getting on with pending to increase security staff
‘what’s in front of us’ and working presence in ED.
with ‘what it is’, especially when
We are delighted to welcome many
we have been working in emergency
new staff – many who have had the
nursing for some time. The thought
additional challenge of joining the
I took away from the session was to
team during COVID restrictions.
be mindful of the changes, choices
We appreciate their input and fresh
and challenges we experienced so
perspectives.
that we can be kind to ourselves as
well as others. Sue
P 18You can also read


