Prime Minister's Challenge Fund Wave Two Learning from wave one
←
→
Page content transcription
If your browser does not render page correctly, please read the page content below
Prime Minister’s Challenge
Fund Wave Two
Learning from wave one

OFFICIAL

NHS England INFORMATION READER BOX

Directorate
Medical                     Commissioning Operations          Patients and Information
Nursing                     Trans. & Corp. Ops.               Commissioning Strategy
Finance

Publications Gateway Reference:                               02635
Document Purpose            Guidance

Document Name               Prime Minister’s Challenge Fund Wave Two - Learning from wave one

Author                      NHS England
Publication Date            08 December 2014
Target Audience             GPs

Additional Circulation      NHS England Regional Directors, NHS England Area Directors
List

Description                 This document is intended to support those who are considering
                            applying to become a pilot in wave two of the Prime Minister’s
                            Challenge Fund. It sets out considerations to help applicants develop
                            highly effective programme and draws on emerging lessons from wave
                            one, as well as the evidence base about large scale service change
                            programmes.

Cross Reference
                            N/A

Superseded Docs
                            N/A
(if applicable)
Action Required
                            N/A

Timing / Deadlines
                            By 16 January 2014
(if applicable)
Contact Details for         Challenge Fund Team
further information         Quarry House
                            Quarry Hill
                            Leeds
                            LS2 7UE
                            0
                            http://www.england.nhs.uk/ourwork/qual-clin-lead/calltoaction/pm-ext-
                            access/#wave2
Document Status
This is a controlled document. Whilst this document may be printed, the electronic version posted on
the intranet is the controlled copy. Any printed copies of this document are not controlled. As a
controlled document, this document should not be saved onto local or network drives but should
always be accessed from the intranet

                                                                                                       2
OFFICIAL

Prime Ministers Challenge Fund Wave Two
Emerging learning from wave one
Version number: 1

First published: December 2014

Prepared by: Dr Robert Varnam, Head of General Practice, NHS England

Classification: OFFICIAL

Publications Gateway Reference: 02635

                                                                       3
OFFICIAL

Contents

Contents ..................................................................................................................... 4
1     Executive summary ............................................................................................. 5
2     Background ......................................................................................................... 6
3     Our shared purpose............................................................................................. 8
4     Engagement to mobilise ...................................................................................... 9
5     Leadership of change ........................................................................................ 11
6     Spread of innovation.......................................................................................... 13
7     Improvement methodology ................................................................................ 21
8     Rigorous delivery ............................................................................................... 23
9     Transparent measurement ................................................................................ 25
10       System drivers ................................................................................................ 28

Annex A – Delivering the technology aspects of your proposal

                                                                                                                              4
OFFICIAL

1 Executive summary
This document is intended to support primary care leaders with planning innovation
programmes. It shares learning emerging from wave one of the Prime Minister’s
Challenge Fund on access to general practice, and existing evidence about
successful large scale change programmes.

                                                                                     5
OFFICIAL

2 Background
In October 2013, the Prime Minister announced a new £50 million Challenge Fund to
help improve access to general practice and stimulate innovative ways of providing
primary care services. Twenty pilot schemes were selected that will benefit over 7.5
million patients across more than 1,110 practices.

The aim of these pilot schemes is to enable NHS England to work more closely with
GP practices up and down the country to promote innovation, share learning and
deliver the benefits to patients of improving access and providing more flexible and
extending access to services. The pilots are exploring a number of ways to achieve
this including:

   •   Longer opening hours, such as 8am-8pm weekdays and opening on
       Saturdays and Sundays.
   •   Joining-up of urgent care and out-of-hours care.
   •   Greater flexibility about how people access general practice
   •   Greater use of technology to provide alternatives to face to face consultations
       eg via phone, email, webcam and instant messaging.
   •   Greater use of patient online services.
   •   Greater use of telecare and health living apps to help people manage their
       health without having to visit their GP surgery as often

The successful bids were built on strong local collaboration among GP practices and
Clinical Commissioning Groups, as well as a responsive approach to understanding
and meeting patient needs. They were required to demonstrate sustainability through
means such as releasing funds from acute care settings as a result of meeting needs
in the community. They have had to mobilise change very rapidly.

Where there are strong relationships between local practices, highly effective
leadership and a robust programme management and technical infrastructure, it
appears that change is quicker to begin. A track record of successful innovation and
trust is therefore a potentially useful predictor of future success.

The chief objective of the Challenge Fund programme is produce evidence for the
NHS about successful innovative approaches to improving access to general
practice. Closely related to this, NHS England’s innovation support programme is
generating actionable learning about how to implement this kind of change across
groups of general practices.

                                                                                         6
OFFICIAL

2.1    Planning for success

Any successful innovation programme depends on both the innovation ideas
themselves (the ‘what’) and the implementation approach (the ‘how’). We wish to
support primary care innovators and commissioners in developing the best possible
approach to both.

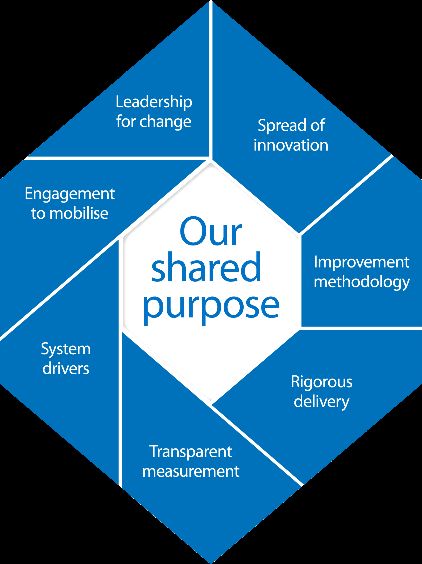
The suggestions here are presented using the
framework of the NHS Change Model
(www.changemodel.nhs.uk). This includes
‘everything we know about successful change in one
place’.

Its 8 components of change provide a comprehensive
framework for planning and learning about change.
Including specific plans in all 8 areas will significantly
increase the likelihood of success. Given that the
evidence shows approximately 70% of large scale
change efforts fail, it is vital that no opportunity to
succeed is overlooked.

 Introductory videos
 A series of short videos walking leaders through top tips for planning is
 available at: vimeo.com/111685786

 A narrated walkthrough of the NHS Change Model is at bit.ly/1jVhA0d

2.2    Innovation support programme
Wave two pilots will benefit from a comprehensive programme of support developed
by NHS England’s national support centre. This is intended to help pilots to create
the best possible plans, make progress as rapidly as possible and gather high quality
evidence and learning for the wider NHS. Pilots will have access to national policy
and innovation experts, as well as a development advisor from NHS Improving
Quality. A programme of workshops, webinars and online discussions will help pilots
to connect and share with one another, and to apply best practice to their own plans.

NHS Improving Quality will also be able to develop a tailored programme of support
for local leaders and practices. Wave one pilots have thus far used this to support
strategic planning, engagement of practices and the public, rapid feedback
measurement approaches, the use of Lean to release staff time, and the
development of local teams of expert service redesign leaders.

More information about the innovation support programme is at
https://vimeo.com/110493143

A national evaluation team was commissioned as part of the innovation programme,
to demonstrate progress, generate evidence about the innovations being tested and
capture key lessons about the conditions for success.

                                                                                      7
OFFICIAL
3 Our shared purpose
Is there a clear purpose for change which is understood by
all participants, and to which all are committed? Does it link
clearly to participants’ underpinning values and the NHS
Constitution? Are all other drivers for change clearly aligned
behind this purpose?
Top tip
Ask each leader to
describe the purpose of
your programme. Do you
have a shared purpose?
• Building shared purpose across participating practices can take a lot of time,
and needs to be an explicit area for action by leaders in the early stages.
• It is often helpful to describe both a case for change (the ‘burning platform’)
and an attractive vision of the future (the ‘burning ambition’). It is usually
necessary to frame this around improving outcomes for patients.
• Shared recognition of the need for change is vital. There are often several
reasons why change is needed, included an aging population, patient
preference for extended access or a need to address health inequalities in the
area.
• Communication to participants often goes straight into describing what is
going to be done, rather than explaining the ‘why’ first.
• As change processes get underway, there is a risk of losing sight of the
purpose. Leaders need to watch out for this and ensure staff energy is
refreshed through repeated restatement of the purpose.
3.1 Practical tips
Bring all your practices together to describe the outcomes you wish to achieve
through this programme.
Include patients and other professional groups in creating this vision of the future.
Identify any important negatives/qualifications (eg “We wish to improve access, while
also promoting continuity of care for people with complex needs.”)
Include a succinct description of the purpose in all communications about the
programme.
8OFFICIAL
4 Engagement to mobilise
Who needs to be part of this change? How are
collaborators being empowered to take action
themselves? How are they contributing to the vision
and plans? What are the plans for making this an
ongoing process?
Top tip
Systematically list the key
people and groups whom you
need to commit to the change.
Why would they want to? How
will you keep them committed?
• Leaders who adopt a bottom-up approach report they develop more
comprehensive plans and make faster progress in securing commitment to
change from participants.
• Inviting patients and the public to engage in shaping plans is strongly
welcomed by them, and practices frequently report being surprised at the
positive tone and practical ideas which emerge. Patients and the public more
often identify ways in which they can be part of the solution, for example
through changing help-seeking behaviours and providing more care and
support in the community.
• Engagement has to be a two-way process, involving not just communication
but practical collaboration. It is quite different from some traditional
approaches to consultation or communication (which is sometimes described
as ‘transmission’).
• Many programmes have found considerable success in creating engagement
through open sharing of data and the application of collaborative planning
tools. Including everyone in the planning stage that is expected to contribute to
the final work is described as key.
• Engaging and mobilising participants takes time, particularly early on.
However, pilots with wide spread buy-in from practices have not had to spend
so much time or resources recruiting and encouraging GPs to be involved in
the pilot.
• A track record of working together is helpful. A large part of this appears to
derive from the deeper level of relationship and trust, and a greater confidence
in the ability of leaders to enact change in a way that is respectful of the past
and people’s values.
9OFFICIAL
4.1 Practical tips:
Ensure every practice is involved in creating the plans, and that communications
about emerging plans are distributed to all staff involved. You may need to
appoint staff specifically as a support team to undertake engagement.. Some
pilots have used ‘discovery interviews’ to gather views of all partners.
Do any parts of the changes you’re proposing require approval, eg via local
scrutiny committee?
Establish regular meetings/action learning sets for ongoing engagement in
service design. For example in Watford, practice managers have formed a
working group to address practical issues and report into the programme steering
group.
If you’re working with a large number of practices, you could appoint link or lead
practices, who are assigned the responsibility to communicate and engage with
other practices in their network or locality. For example in North West London
each network will identify a GP lead to act as a link for local practices.
Consider bringing in expertise in patient and public engagement. Involve local
people in developing your priorities, designing better services and monitoring
progress.
A multi-faceted approach is usually required, using a selection of engagement
techniques such as roadshows, workshops, surveys, newsletters and social
media.
10OFFICIAL
5 Leadership of change
Who is leading this change? How widely is leadership
being shared among participants? Does everyone who
can contribute as a leader know that they are expected
and encouraged to lead? Do they have the skills and
support required to engage, inspire and support others?
How is their time being protected? What is the plan for
bringing in new leaders?
Top tip
Identify your key leaders, and
provide protected time for them
throughout the programme.
Multi-practice collaborative
change does not ‘just happen’.
• Many of the pilots are led by inspirational professional leaders who attract the
confidence and commitment of practices. A tremendous resource of creativity
and determination is being brought to the programme by these leaders.
• Another key component of their effectiveness is the deep understanding of the
realities of primary care. Where people are brought in from outside, they are
able to operate as effective managers, but appear to have less success as
leaders.
• Programmes appear to get started more quickly and to maintain momentum
best when the leaders understand from the outset that their role includes
leading as well as planning, and where time is set aside for them to lead. This
often requires a plan and budget to backfill their time, which can take a long
time to establish. Where leaders are not able to devote a significant proportion
of their time to the programme, even well-developed plans can stall.
• Leadership of change across practices often falls to a small number of people.
These are often tremendously able – but nevertheless find it very challenging
to maintain the energy of the large number of people involved in the
programme. This is less of a problem where there is a strategy for explicitly
sharing leadership responsibility across a wide group.
• Key personnel often need to attend to managerial duties in the change
programme, but are most successful when they combine this with
transformational leadership practices such as engaging in continual open
dialogue and maintaining everyone’s focus on the shared purpose for change.
• The leadership challenges most often cited by pilots are engaging and
inspiring others’ commitment, handling conflict and maintaining energy for
themselves and their immediate team.
• Few primary care leaders have received formal training in leadership, but most
value it when offered in a relevant and appropriate way. Few have well
established peer support networks, either, but welcome opportunities to build
them, especially once change is underway. Planning in advance for leaders’
11OFFICIAL
support and personal development needs is therefore an important part of
initial programme planning.
5.1 Practical tips:
Senior leaders need to get practice agreement to dedicate time to developing
plans and implementing them if successful. Experience shows this cannot be
done in the margins of existing commitments.
A regular meeting of senior practice representatives is a popular means of
maintaining engagement and sharing leadership duties. Consider in advance how
to cover clinical time for such meetings.
Separate ‘task and finish’ groups can be created, to share work and broaden
engagement.
Depending on your plans, it may be helpful to establish wider sponsorship and
steering arrangements. Many wave one pilots have included representatives of
CCGs, the LMC, the area team, local authority, and leaders from social care and
the voluntary sector.
Many pilots have booked selected local leaders onto a ‘change agent’ training
programme provided free by NHS Improving Quality. This will build confidence
and skills to accelerate progress, as well as leaving a legacy of improved
capability for advanced change leadership in the locality.
12OFFICIAL
6 Spread of innovation
What is the approach to seeking and applying evidence
from elsewhere? How will other innovations be adapted
for local use? What methodology is planned for rapid
innovation testing and refinement, and for innovations to
be rolled out across all participating practices once they
are refined? Where challenges are encountered, what
creative thinking approaches will be used, to find
solutions? How will learning and evidence be gathered,
to allow others to see the benefit of your innovations and
to apply them for themselves?
Top tip
People may be unique, but the
challenges of leading change
are not. Learn from others'
practical experience with
similar work to yours.
There is a wealth of innovative ideas in primary care, and leaders sometimes
need only to create a small amount of space for staff to unleash their creativity.
However, it is easy to underestimate the number of practical challenges which will
arise, and others’ prior experience can be invaluable. There are some key general
principles demonstrated by the PMCF pilots’ experience thus far.
• Although each local context has its unique features, most of the lessons which
could be learned from other places have at least some relevance. Setting
aside regular time to share experience and ideas with other innovators can
help leaders make much faster progress on their own work. Pilots have often
been able to use a ready-made solution from another team, and have found
regular peer-to-peer networking invaluable. Those who have been less
engaged have sometimes devoted a lot of time to reinventing their own wheel.
• Gaining commitment to adopt innovations is easier and quicker where there is
a track record of innovative working and collaboration. It is also facilitated by
local expertise in innovation practice, including rapid cycle testing and
measurement. Both refining and rolling out innovations is quicker where a
systematic approach is used, including the availability of funding for staff time
in practices.
• While innovations in care are generally presented singly, the greatest success
often comes when they are combined. This is partly to achieve a wider
programme of change towards a common goal, and partly to capitalise on
synergies between specific innovations. This is most helpful when changes in
one aspect of care might have an impact on other aspects, either positive or
negative. Challenge Fund pilots have combined large numbers of discrete
innovations into programmes intended to achieve more than the sum of their
parts, while mitigating many anticipated risks.
13OFFICIAL
• Taking a fresh look can identify ways in which even previously failed
innovations can be effective. In such situations, it is commonly found that
previous attempts did not include sufficient adaptation of an idea to work in the
local context or a lack of leadership success in achieving staff buy-in.
• Primary care innovators do not always have a strong interest in documenting
their work. However, without a record of what was done, how and with what
impact, others are unlikely to copy their work, even in neighbouring practices.
14OFFICIAL
6.1 Collaborative working
Many high impact innovations involve professionals and organisations working
together in greater collaboration. There are a number of important issues to attend to
in order to ensure such changes work safely and effectively. Most pilots are using
this as an opportunity to further develop local networks and federations,
strengthening their effectiveness for the future. It is common to discover that much
needs to be done, to turn an existing federation into an organisation ready to deliver
wider primary care at scale.
Pilots are finding that many of the issues below are easier to address if a single
organisational entity is created to act as the coordinating hub of collaboration and
new service provision across participating practices. This facilitates the holding of a
contract for the Challenge Fund work, registration with the Care Quality Commission,
and the creation of common approaches to issues such as governance and care
processes. Other arrangements such as having a single lead practice are preferred
by some pilots.
6.2 Organisational form
Many wave one pilots have set up new legal entities, registered with Companies
House in order to deliver the new care they planned. This provided an easy means
for them to receive the grant money within the Challenge Fund programme. It also
allowed them to employ staff, reduce risks for the practices involved, share
responsibility and in some cases begin to bid for other work eg. community services.
Discuss this possibility with your practices in advance, as the decision making
process and subsequent organisational processes take time and resource.
Where possible, use this as an opportunity to develop existing collaborative
relationships, establishing wider primary care at scale for the future.
You will need to create new corporate governance capacity and procedures, ensuring
best practice and legal compliance.
15OFFICIAL
6.3 Workforce development
New ways of working and new organisational forms usually have implications for
staff. GP practices do not always have experience in managing significant HR
changes, so it is worth explicitly planning for this aspect of your programme.
New recruitment. Who will you need to recruit? How much time will it take to have
new staff in place? Most pilots have recruited new management staff, as well as
secured additional input or extended roles for existing staff.
Be realistic about the likelihood of being able to recruit additional GPs or nurses to
work on a new programme. Wave one pilots have generally progressed faster where
they have used existing staff from local practices. Some have actually found that the
programme has made it easier to retain staff in the area.
Secondments, shared rotas, transfers and extended roles. What are the practicalities
of arranging these safely and legally? Do you need to consider TUPE regulations?
How will you arrange training and ongoing support for staff undertaking new roles or
working in new ways? Who will be responsible for such HR issues within your
programme?
6.4 Information governance
Providing more joined-up care requires greater sharing of information between
professionals. It is important to have a plan for how to ensure appropriate safeguards
are in place to protect patient confidentiality while doing this. It will be necessary for
all practices and clinicians involved in a new collaboration to approve the governance
arrangements.
It is important to ensure patients are well informed about the move towards
collaborative working, including clear messages about the intended benefits and the
safeguards in place. Patients themselves expect the NHS to provide better access
and more joined-up care, and are often enthusiastic champions for these innovations
when given the opportunity.
Most pilots are using NHS smartcards to authorise access to the patient's own
practice when consulting out of hours, accompanied by obtaining the patient's
consent on each occasion they consult an extended hours service.
One approach for creating robust governance involves each clinician involved in
providing extended hours care having an honorary locum contract with every practice
in the local cluster.
Every organisation taking part in a pilot project should be accredited as being at level
two or above on the current Information Governance Toolkit, or give assurance of
robust plans that are in place to be compliant before the pilot goes live.
NHS England will be producing updated information governance guidance in
December 2014 that will consider new care models enabled through technology.
16OFFICIAL
From December, PMCF pilots will also have access to IG support from NHS
England’s national patients and information directorate.
Further guidance on Information Governance issues that may be relevant to
applicant projects is available at:
http://www.england.nhs.uk/ourwork/tsd/ig/
https://www.gov.uk/government/uploads/system/uploads/attachment_data/file/37193
2/OE_010079_IGA_Staff_Leaflet_A4_Lanv7_A-W_Final_Single_pg-Web.pdf
http://systems.hscic.gov.uk/infogov
6.5 Clinical governance
Collaborative working poses new questions about clinical governance for general
practice. Pilots are finding it important to establish a new level of relationship, trust
and shared working between practices and individual professionals.
Agree early on with participating practices how you want to arrange clinical
governance when collaborating in this programme.
This often involves regular meetings in which all participants share in decision
making. This takes leadership commitment.
A number of pilots are also introducing shared training and audit across collaborating
practices, supported by more common working practices and cluster-wide
governance agreements. Sometimes these are reinforced by individual agreements
by individual clinicians with the cluster as an entity, supplementing those already in
place with their own practice.
6.6 Indemnity cover
Providing care for patients registered with another practice, or in additional hours,
requires GPs and nurses to obtain additional professional indemnity cover. This is
usually charged at a higher rate. Pilots have found that some insurance companies
are more responsive and flexible than others when approached with regards to
securing additional cover.
Find out early on who your clinicians are currently covered by, and how much it will
cost to extend their cover to include this work.
For some nurses, the additional premiums could be considerable in comparison to
their current cover.
You may need to shop around to find a company able to meet your needs.
6.7 CQC registration
17OFFICIAL
Changes to the type, location or staffing of a service will often have implications for
the provider’s registration with the Care Quality Commission. They will be providing
new guidance in late 2014 to advise providers on the issues involved. A key lesson
emerging from the Challenge Fund is that services provided through a new entity
such as a GP federation should be assumed to require a new registration with the
CQC.
Make early contact with the CQC registration manager for your region to discuss the
changes that might be necessary. They will be able to advise on whether a new
registration will be needed.
Once new registration forms are submitted, it is advisable to allow up to 2 months for
registration to be confirmed.
6.8 Information technology
Lessons are emerging from the PMCF about innovations in the use of information to
improve access. Innovations being tested include the sharing of patient records
between local GP practices and other providers, online and video consultations, and
personalised signposting systems using websites and mobile telephone health apps.
Insights have been gained into the process for deploying these.
The key practicalities to consider are as follows:
6.9 Timescales
It can take a considerable amount of staff time to plan and implement new IT
solutions, especially where multiple suppliers or providers are involved (as is often
the case in general practice innovation). It is best to plan a small scale trial of any
new solution before rolling it out across a large number of providers. Many innovators
find a large number of issues which need to be ironed out in order to deploy a new
technical solution safely, effectively and efficiently. For example, projects which aim
to perform a wholesale replacement of IT systems across an entire CCG estate, or
which require long and complex procurement processes to be successful may be
considered a high risk for non-delivery. Failing to address these before full roll-out
may pose a significant threat to patient care or staff time, and will impact the trust
placed in you by participating practices.
Undertake a detailed planning process that seeks to review the technology
options and associated business change to anticipate as many of the practical
challenges and interdependencies as possible. It’s important to develop a
robust technical delivery plan that demonstrates the appropriate capacity and
capability of both the practice and suppliers at the outset,
Allow sufficient time in the programme plan for working through planning,
procurement, technical installation and implementation to accommodate new
ways of working.
Consider securing your own primary care IT expertise to help with negotiating
with suppliers, procurement/contract management and maintaining a rigorous
18OFFICIAL
approach to project implementation.
Where possible, plan to test any new solution on a small scale before roll-out.
Where this is not possible, it is worth considering simulating or ‘walking
through’ key aspects of the new solution, to identify important snags to be
addressed before roll-out.
Annex A provides further information on delivering the technology aspects of
proposals. This annex describes the types of issues that practices will want to
consider in order to make their pilots a success.
6.10 Interoperability
There is a wide range of existing IT systems already in place, and many innovations
involve introducing new ones. There is a need to consider how a proposed new
solution will work alongside existing systems and the architecture of partner
organisations to allow interoperability across other parts of the health and care
system. Achieving safe and seamless communication between systems is critical to
the success of many programmes seeking to improve patient care. In particular, most
new models of access require collaboration between GP practices and other
providers, including the sharing of patient records. This improves patient safety and
allows providers other than the patient’s GP practice to provide more appropriate
clinical care.
To achieve this sharing of information requires the need to use common standards
for information sharing. These are:
Use of the NHS Number as the primary identifier for all correspondence and
its use to track all activity of a patient within primary care but also within the
organisations that information is being shared with.
The use of systems that have “Open Application Interfaces” which means that
systems can share information openly. NHS England has created a policy to
explain what this means and what is expected from IT system suppliers. 1
The use of existing interoperability specifications (Interoperability Toolkit- ITK)2
for information sharing. In particular, for joining up of urgent care and out-of-
hours care:
o Clinical Correspondence (Electronic Discharge Summary) ITK
specification
o Health and Social Care ITK specification
o 111 ITK specification
o Telehealth ITK specification
Use of robust identity verification approach (including face to face) for access
to records in primary care.
To communicate with colleagues and patients through online conferencing
should use industry standards, e.g) SIP, XMPP, WEB RTC.
1
http://www.england.nhs.uk/ourwork/tsd/sst/the-open-api-policy/
2
http://systems.hscic.gov.uk/interop/background/specs
19OFFICIAL
In addition, the use of existing national offerings that support Interoperability such as
the NHS Mail (or ISO27001 accredited local system) is used for emails containing
patient-identifiable data, Summary Care Record, Electronic Prescription Service and
GP2GP.
As an implementation of advanced capability, practices are also encouraged to
implement the clinical endorsed headings from the Academy of Medical Royal
Colleges when sharing clinical documents. 3
Further references to support how using data and technology to transform outcomes
for patients and citizens can be found in the recent publications of; ‘Personalised
Health and Care 2020’ https://www.gov.uk/government/publications/personalised-
health-and-care-2020 and the NHS ‘five year forward view’
http://www.england.nhs.uk/ourwork/futurenhs/
Further expert support
NHS England’s national information technology and governance teams will be
working alongside pilots to provide ongoing support through advice and guidance
during wave two pilots to ensure robust technical delivery plans are in place from the
outset.
Additionally, NHS England is hosting two workshops to support effective planning for
the IT components of proposed Challenge Fund programmes.
15th December 2014, 9:40am – 4:00pm
30 Euston Square, 1 Melton St, London NW1 2FB
Register at www.events.england.nhs.uk/nhs-england/288
18th December 2014, 9:40am – 4:00pm
Park Plaza Hotel, Boar Ln, City Square, Leeds, Yorkshire LS1 5NS
Register at www.events.england.nhs.uk/nhs-england/287
Further information is available from england.digitalprimarycare@nhs.net.
3
http://www.infostandards.org/category/areas-of-interest/cdgrs/
20OFFICIAL
7 Improvement methodology
What improvement methodology(s) will be used to help
redesign and improve systems and processes of care?
How will practices be supported to work smarter, not just
harder, in the implementation of these changes? What
skills, tools and infrastructure would need to be in place
to make best use of approaches such as PDSA or Lean?
Top tip
Use expert service redesign
support to release staff
capacity before introducing any
new systems or processes.
• High level ambitions are turned into successful change most effectively,
rapidly and sustainably when a systematic approach is taken to implementing
change at the level of processes within practices.
• The details of this are commonly overlooked in primary care innovation, with
assumptions being made about the ease with which change can be made.
• Methodologies such as the Model for Improvement, Lean and 5S are proving
very successful at releasing staff capacity through waste reduction, and
embedding change more successfully through a systematic team-based
approach. Many pilots are finding it important to find ways of releasing staff
capacity early on, and programmes such as The Productive General Practice
are proving a popular means of achieving this.
• The lack of experience in using these improvement tools in most practices
means that people have often become used to assuming that all change
involves working harder, longer or faster. This presents both a cultural and
practical brake in innovation programmes.
• Early planning of how improvement methodologies can be used in a change
programme allows leaders to secure appropriate expertise or training. This
can create added value by leaving a legacy of increased service redesign
capability in the locality, as well as increasing staff satisfaction.
• Where one or more practices in a locality have prior experience, it is much
easier for neighbouring practices to appreciate the potential benefits of
improvement methods. Arranging early conversations to share this experience
is therefore very helpful. Where this is not possible, it is advisable to connect
with peers from elsewhere who can discuss these methods.
• A small but growing number of products and services are available which
support practices through the process of applying improvement tools to their
work or to specific aspects of their practice. Although these can be used in
isolation, they seem to be both more attractive and more effective when
deployed in collaboration between local practices and in the service of a
programme of change with a clear patient benefit.
21OFFICIAL
7.1 Practical tips
As you develop the specification of your new service, identify areas where a new
system or process will be necessary. How will this be designed and refined? How will
you ensure it is reliable and safe, as well as effective and efficient?
Consider what changes will be needed to the way other parts of the system operate.
What handovers of care are required, or changes in consulting behaviours? How will
they be designed and refined?
Do any of your practices have experience of using improvement methods such as the
Model for Improvement or Lean? Seek their advice about getting the most from them.
Consider getting advice from an improvement expert about how to apply best practice
in improvement science in your programme.
Programmes such as The Productive General Practice from NHS Improving Quality
can make a very effective adjunct to your change, helping to release capacity, build
teamwork and create a fresh sense of possibility.
NHS Improving Quality’s primary care team will be providing free advice to support
your planning through webinars in the winter of 2014. Details will be listed at
http://bit.ly/pmcf2news
22OFFICIAL
8 Rigorous delivery
What approach will be used for programme planning and
delivery? What assurance is there that all participating
providers will be consistent in following the programme’s
management? Does the approach reinforce shared
purpose and build on core values? How much
management staff time will be needed? What
opportunities are being used to achieve economies of
scale and efficient working across the programme?
Top tip
Budget for additional
management capacity, rather
than expecting practice staff
to find extra time.
Running a large multi-site innovation programme at pace is a significant programme
and project management challenge. It often involves activities outside the experience
and capacity of many managers in general practice. The experience of PMCF pilots
is illustrating these issues.
• The speed with which complete and robust programme and project plans are
in place depends largely on the time devoted to management and the level of
prior experience in the managers involved. A number of pilots have included
external managers with expertise in larger programme, and this has proved
helpful, particularly where they are embedded as part of a well functioning
programme leadership team.
• Developing an excellent, realistic and actionable plan is usually an iterative
process. Leaders should expect this and allow sufficient time.
• External review and advice is helpful in improving plans. In particular, it can
identify areas where likely challenges could better be anticipated, and where
different leadership approaches can be considered. In practice, constructive
external review often results in more detailed plans being produced, with more
realistic estimates of timescales and budgets. It also results in a greater
emphasis on ways of creating and maintaining engagement, and of using
improvement science to ensure the most efficient and effective solutions are
reached.
• Most plans need multiple changes once a programme is underway, and
managers should be allowed the time to undertake ongoing monitoring and
revision of details.
• The unexpected always occurs, and successful managers plan contingencies,
particularly in the areas of timescales, budgets and workforce.
• Innovation programmes often present challenges to existing management
capacity or business infrastructure. It is worth being proactive about seeking
evidence during the programme of areas where additional work is needed.
These programmes are also an excellent opportunity to create a legacy of
23OFFICIAL
increased capabilities in local practices, and leaders are encouraged to find
ways to achieve this, rather than relying entirely on external management
support.
• Please ensure there are clear plans for ongoing benefits realisation. An easy
mistake to make is that once a programme is successfully set up, the job is
done. In many ways that is when the real work starts on ensuring the benefits
to patients are delivered.
8.1 Practical tips
Allow time to develop a detailed programme plan, before then reviewing the
likely project management time and skills necessary to implement it.
Consider different areas of specific need such as HR, finance, legal, IT,
governance and operations management.
Consider obtaining external review of the plans and estimates for likely
management needs.
Ensure you are not relying on unfunded time from participating practices.
Consider how individual sub-programmes could be created, to progress
specific pieces of work. This also presents an excellent means of building
practice engagement.
24OFFICIAL
9 Transparent measurement
Have goals been articulated as measures? Are measures
being used which will stimulate curiosity, drive
improvement and demonstrate progress? Do you have
measures which will evaluate processes, outcomes and
potential adverse consequences? Is qualitative data
being used alongside quantitative, to yield additional
understanding and insights into staff and patient
experience? Are continuous statistical methods used, to
provide realtime feedback? Does everyone we want to
see and be influenced by our data have easy access to it
in a meaningful format?
Top tip
Have a plan and budget
for measurement – it
doesn’t just happen.
Innovation cannot successfully be developed and spread without data. Yet
measurement remains a frustrating issue for many innovation programmes. Some of
the most common reported challenges are a difficulty in obtaining the right data,
distractions created by gathering the wrong data, a lack of timely feedback of results
and uncertainty about which metrics will drive the best results.
• Innovation leaders often wish to gather a large number of different metrics.
These generally cover aspects of processes and outcomes. In practice, the
time cost of gathering data often requires compromises to be made. However,
it is usually possible to agree a manageable number of metrics which will
satisfy all key needs.
• In the PMCF, peer-to-peer discussions among the pilots, together with
measurement and improvement experts has proven helpful in designing
metrics. It has also demonstrated the value of allotting sufficient time to
planning for successful measurement.
• It is easy to overlook potential adverse consequences in choosing what to
measure. Yet this is important, to protect patients, ensure efficiency and
maintain staff engagement.
• Gathering data often involves a significant amount of staff time. It is worth
considering in advance what support and tools will be needed for practices,
and how comprehensive data gathering will be incentivised.
• Qualitative data such as patient views often provides unique insights which
address many of the issues staff care most about.
• Local people can be very effective champions of primary care innovation, and
this can be strengthened by keeping them updated on progress. The local
press are often very interested, too, and may be a key channel for informing
people about your work, for example through regular updates.
25OFFICIAL
• There is limited experience of using statistical analysis techniques suited to
rapid feedback, so it is worth obtaining expert advice on this, for example from
NHS Improving Quality.
• Most local areas do not have access to business intelligence tools to support
multi-practice data gathering and analysis. A system has therefore been
created for the PMCF to do this.
9.1 Practical tips
Agree the key questions which will need answering in order to monitor progress,
demonstrate impact and maintain staff enthusiasm. Work up suggested ways of
measuring these, and test the practical implications of gathering the data.
Plan for how data will be gathered throughout the programme. Include estimates of
the staff time required. Check these with practices, and reach agreement about how
to fund the time or provide additional staff time.
Ensure data collection, analysis and presentation is included in the budget.
Plan for how data will be gathered and fed back sufficiently rapidly to maintain the
interest and motivation of practices.
Ensure you are using analysis tools which provide statistical process control for
continuous analysis.
9.2 National metrics
An extensive programme of coproduction was undertaken with wave one pilots to
develop a small number of metrics for the quantitative arm of the evaluation. These
are as follows:
Patient contact, as a direct result of the change in access
1. The change in hours offered for patient contact;
2. The change in modes of contacts;
3. The utilisation of additional hours offered; and
4. Impact on the ‘out of hours’ service.
Patient experience/satisfaction, including patient choice
5. Satisfaction with access arrangements; and
6. Satisfaction with modes of contact available.
Staff experience/satisfaction
7. Satisfaction with new arrangements
Wider system change.
8. Impact on the wider system attendances
9. Impact on emergency admissions
In addition to these, a rolling programme of qualitative evaluation is being used. This
involves an evaluation manager being assigned to each pilot and engaging closely
with them throughout the programme to gather information about each step of
26OFFICIAL
change. This allows rapid identification of issues which the national support team to
address, detailed case studies of progress and patient and patient experience, as
well as a comprehensive understanding of key success factors.
27OFFICIAL
10 System drivers
How does this innovation align with the priorities of local
strategy? Does the environment within which practices and
staff operate make it easy to develop and implement
innovations? Do the culture, incentives and management
encourage the changes being promoted? How do
commissioners and system leaders learn about what could
be done to make positive change easier for innovation
leaders? Are there new skills, information, tools,
relationships or resources needed in order for these changes
to be adopted sustainably?
Top tip
See successful and sustainable
innovation as a partnership between
commissioners and providers. And then
plan together.
A great deal can be achieved by determined innovators, even working alone.
However, for change to be spread and sustained almost always requires a conducive
environment. Factors such as financial incentives (or disincentives), workload, a lack
of trained staff or information can all impede change.
• In addition to the way in which services are commissioned, other system
drivers identified as important by the pilots so far have included the following.
o Information technology. As discussed above, while much can be
achieved within existing systems, new collaborative services require
updated software and improved access to hardware in some providers
(eg community nursing or care homes) if they are to flourish.
o Information governance. As discussed above, new structures,
processes and rules may be required to provide the kind of joined-up
care patients increasingly need.
o Workforce. In addition to increased numbers of GPs and practice
nurses, innovators are interested in using staff such as community
pharmacists, therapists and care and support workers, to deliver new
models of care.
o Collaborative culture. Even where positive relationships have existed
between GP practices for many years, the kind of shared working
required by some new care models has required a new level of trust
and collaboration. Achieving this has often taken a considerable
investment of leadership time and skill.
• Addressing system issues which impact one specific piece of innovation such
as the PMCF frequently has much wider benefits. For example, creating new
information sharing infrastructure and agreements will allow more coordinated
care, improving patient safety, clinical effectiveness and efficiency.
28OFFICIAL
• Intentionally aligning one change programme with others in the locality, while
usually involving additional work in the planning stages, can allow for wider
and more sustainable progress, often with less work in the implementation
stages. Many PMCF pilots have closely aligned their work with programmes
involving IT, integrated care, long term conditions or urgent care.
10.1 Practical tips:
Deliberately seek existing networks and initiatives to use and/or align with in
undertaking your change programme.
Seek to develop your plans in close collaboration with as many other key
system partners and subject matter experts as possible, to make best use of
potential synergies and build a larger coalition for change.
Create mechanisms for ongoing dialogue between the innovation leaders and
local commissioners.
Develop plans with commissioners for how successful innovations can
become sustainable beyond the life of the pilot programme.
29OFFICIAL
30You can also read


